
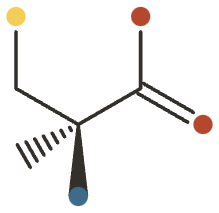
L-Cysteine
L-Cysteine is a sulfur-containing, semi-essential amino acid and the rate-limiting precursor for glutathione; it is most often supplemented as its stable derivative NAC.

L-Cysteine at a Glance
L-Cysteine is a sulfur-containing, conditionally essential amino acid whose entire pharmacology turns on a single reactive thiol (–SH) group. It is the rate-limiting substrate for glutathione — the body’s principal intracellular antioxidant — and a precursor to taurine and coenzyme A. The body makes it from the essential amino acid methionine, so it becomes dietarily essential only when methionine is low or demand is high.
Two distinctions decide how to read everything below.
The first is repletion versus addition. Correcting a cysteine or glutathione shortfall — in malnutrition, ageing, critical illness — is real and measurable. Taking extra on top of adequate protein is where the human signal largely disappears.
The second is form. Free L-cysteine is rarely what was actually studied. It oxidises readily to cystine and can turn pro-oxidant at high doses, so the clinical literature overwhelmingly uses N-acetylcysteine or the disulfide L-cystine instead. Read the evidence below as evidence for cysteine delivery, with the form named each time — not as evidence for swallowing free cysteine.
What It’s Used For
- Glutathione & antioxidant repletion — the best-supported use, and only where glutathione is actually depleted.
- Hair quality & shedding — from L-cystine + B-vitamin combination trials, not free cysteine.
- Skin lightening & pigmentation — one trial, and the effect needed the L-cystine + glutathione pairing.
- Appetite & satiety — a single acute human experiment inside a mostly rodent study.
Not supported: general “antioxidant” and “detox” claims for free L-cysteine in healthy, well-nourished people. And a counterweight worth holding — higher plasma cysteine tracks with adiposity and cardiometabolic risk in observational data, so “more is better” is not a safe assumption here.
How It Works
Everything begins at the thiol. Cysteine’s –SH group is reactive enough to scavenge radicals directly and to form the disulfide cross-links that give keratin its structure — which is the mechanistic basis for the hair and nail claims, since cysteine is the most abundant amino acid in keratin.
Its more important job is upstream of glutathione. GSH is a tripeptide of glutamate, cysteine and glycine, and cysteine is the step that limits the rate — not the other two. That single fact explains the shape of the evidence: restoring cysteine raises glutathione when glutathione is short, and does very little when it isn’t. Supply, not dose, is the driver.
Downstream, cysteine is the precursor to taurine and coenzyme A, and via glutathione it skews melanin synthesis toward the lighter pheomelanin — the proposed route for the skin-lightening effect.
The instability is worth restating as mechanism, not trivia: free cysteine auto-oxidises, and at high concentrations that makes it a source of oxidative stress rather than a defence against it.
The full trial record is in Pharmacology & Research below.
Pharmacology & Research
L-Cysteine is a sulfur-containing, conditionally essential amino acid whose entire pharmacology turns on one reactive thiol (–SH) group: it is the rate-limiting substrate for glutathione (GSH), the body’s principal intracellular antioxidant, and a precursor to taurine and coenzyme A. The decision-relevant distinction here is between correcting a cysteine/GSH shortfall — which is real and measurable in malnutrition, ageing, and critical illness — and taking extra on top of an already-adequate protein intake, where the human signal largely disappears. A second caveat runs through almost every application: free L-cysteine is rarely the form studied. It oxidises readily (to cystine) and can be pro-oxidant at high doses, so the clinical literature overwhelmingly uses the more stable derivative N-acetylcysteine (NAC) or the disulfide L-cystine. Read the evidence below as evidence for cysteine delivery, with the form named in each case, not as evidence for swallowing free cysteine specifically.
Support is an experimental score I’m building — a composite weighted by study type (human > animal > in vitro > review) and study volume. It’s a beta: a fast way to rank strength of evidence at a glance, not a validated metric. Each application links down to its write-up.
Cysteine availability, not glycine or glutamate, is the rate-limiting step in glutathione synthesis, so restoring cysteine supply raises GSH when — and largely only when — GSH is depleted. In older adults, the GlyNAC trials (glycine + NAC as the cysteine source) are the strongest human data: a 16-week placebo-controlled RCT (n=24 older adults, isonitrogenous alanine placebo) corrected GSH deficiency and oxidative stress and improved mitochondrial function, insulin resistance, gait speed, muscle strength and systolic blood pressure 1,
A separate dose-ranging RCT in 114 healthy older adults confirmed GlyNAC (2.4–7.2 g/day, 2 weeks) improved GSH redox status and oxidative-damage markers 5Reference 5RCTA randomized controlled clinical trial in healthy older adults to determine efficacy of glycine and N-acetylcysteine supplementation on glutathione redox status and oxidative damage — randomized controlled trialView study →.
In edematous childhood malnutrition, isotope-tracer work shows GSH synthesis is cysteine-limited, and supplemental sulfur amino acid is needed to meet demand 4Reference 4RCTEffects of randomized supplementation of methionine or alanine on cysteine and glutathione production during the early phase of treatment of children with edematous malnutrition — randomized controlled trialView study →.
The consistent pattern is repletion: benefit appears where cysteine/GSH is short, and the trials use NAC — not free L-cysteine — as the delivery form.
Gap: almost no controlled data on free L-cysteine itself, and no convincing GSH or clinical benefit in healthy, replete adults; the effect is deficiency-dependent and confounded by co-supplemented glycine.
Cysteine is the most abundant amino acid in keratin, which is the mechanistic basis for using it in diffuse hair shedding (telogen effluvium). Two older randomised, double-blind, placebo-controlled trials tested an oral L-cystine + B-vitamin combination: a 4-month study in 72 women found the L-cystine-containing product significantly improved anagen (growth-phase) rates and hair quality versus placebo 6Reference 6RCTSystemic therapy of diffuse effluvium and hair structure damage — randomized controlled trialView study →, and a second 4-month RCT in 60 patients reported improved trichogram and hair-quality measures with active treatment over placebo 7Reference 7RCTThe efficacy of drug therapy in structural lesions of the hair and in diffuse effluvium — comparative double-blind studyView study →.
Both tested the combination product, not free L-cysteine, and both are small, dated, and tied to the manufacturer.
Gap: no isolated free-L-cysteine trial; the effect is attributed to a multi-ingredient formula (L-cystine + thiamine + pantothenate), the studies are small and old, and there is publication and sponsorship bias.
Glutathione is a proposed skin-lightening agent — it skews melanin synthesis toward the lighter pheomelanin — and cysteine feeds that pathway. A 12-week randomised, double-blind, placebo- and benchmark-controlled trial in 124 Asian women compared 500 mg L-cystine + 250 mg reduced glutathione, glutathione alone, L-cystine alone, and placebo. The combination produced significant skin lightening and reduced facial dark-spot size, and outperformed either single ingredient 8Reference 8RCTThe effects of the oral supplementation of L-cystine associated with reduced L-glutathione-GSH on human skin pigmentation — randomized controlled trialView study →.
The single-ingredient arms did not reproduce the effect.
Gap: one industry trial in one narrow population with a cosmetic endpoint; the effect requires the L-cystine + glutathione pairing, and it does not generalise to free L-cysteine or to health outcomes.
L-cysteine was identified as the most anorexigenic amino acid in a screen, plausibly contributing to protein-induced satiety. In the human portion of a predominantly rodent study, oral L-cysteine reduced subjective hunger and suppressed plasma acyl-ghrelin; in rodents it dose-dependently cut food intake, delayed gastric emptying and increased brainstem neuronal activation 9Reference 9AnimalL-cysteine suppresses ghrelin and reduces appetite in rodents and humansView study →. This is a single acute human arm with no body-weight endpoint.
Gap: no chronic human trial and no weight-loss outcome — the human evidence is one small acute mechanistic experiment, so this is hypothesis-generating only.
Mechanisms
| Target / pathway | Effect | Relevant to |
|---|---|---|
| Glutathione (GSH) synthesis | Rate-limiting substrate (γ-glutamylcysteine step) | Antioxidant repletionageingimmune |
| Thiol/disulfide (–SH) redox | Direct radical scavenging; cellular redox buffering | Antioxidantgeneral oxidative stress |
| Keratin disulfide cross-links | Structural cysteine incorporated into hair and nail protein | Hair & nail quality |
| Melanogenesis (via GSH) | Skews melanin toward lighter pheomelanin | Skin pigmentation |
| Acyl-ghrelin suppression | Lowers orexigenic ghrelin; delays gastric emptying | Appetite/satiety |
| Taurine & coenzyme A synthesis | Cysteine is an upstream precursor | Downstream metabolic roles |
Pharmacokinetics
Free L-cysteine is absorbed in the small intestine but is chemically unstable — it auto-oxidises to cystine and can act as a pro-oxidant at high concentrations, which is the practical reason supplements and trials favour NAC (deacetylated to cysteine intracellularly) or the disulfide cystine. Plasma cysteine is tightly homeostatically controlled, and much of an oral load is oxidised, incorporated into protein and glutathione, or catabolised to sulfate and taurine; the plasma half-life of free cysteine is short, on the order of a couple of hours. Because glutathione output is substrate-limited only when cysteine is scarce, raising intake above adequacy produces little extra GSH in replete people — the driver of benefit is baseline deficiency, not dose.
Clinical trials
Free L-cysteine itself is off-patent, cheap, and attracts almost no dedicated industry trials. The registered-trial activity clusters around NAC — hundreds of trials across respiratory, psychiatric, hepatic and toxicology indications — and the GlyNAC combination for ageing. Dedicated trials of the free amino acid are rare and mostly small.
| Completed | Planned | Terminated | Preclinical |
|---|---|---|---|
| ~6(free cysteine/cystine) | 1–2 | 0 | ~30+ |
Last checked: August 2026.
Dietary Sources
Cysteine is supplied by essentially all high-protein foods, and the body also makes it endogenously
from the essential amino acid methionine via the transsulfuration pathway
— so outright deficiency is rare in people eating adequate protein. It becomes limiting mainly when
protein or methionine intake is low, or when demand rises: prematurity, severe illness, ageing
4,
| Food (typical serving) | Approx. cysteine |
|---|---|
| Chicken/turkey breast (100 g) | ~350–400 mg |
| Beef/pork (100 g) | ~250–350 mg |
| Fish (100 g) | ~250–300 mg |
| Lentils/beans, cooked (1 cup) | ~150–250 mg |
| Oats, dry (½ cup) | ~150 mg |
| Egg (1 large) | ~130 mg |
| Sunflower seeds (30 g) | ~130 mg |
| Cheddar cheese (30 g) | ~90–100 mg |
| Milk (1 cup) | ~70–80 mg |
Values are approximate and vary with cut, variety and preparation. There is no ODS fact sheet dedicated to cysteine — it is covered within protein and amino-acid requirements.
Cooking and processing that degrade protein quality lower the delivered amount, as does refining that strips the protein-rich germ and bran from grains. Digestibility of protein-bound cysteine from cooked animal and legume foods is high, roughly 90% or better.
Intake & Dosage
These are amounts studied in research and general reference values — not a personal recommendation.
- Requirement: cysteine has no separate RDA. Requirements are set for total sulfur amino acids (methionine + cysteine) at about 19 mg/kg/day in adults — roughly 1.3 g/day for a 70 kg person, most of which a normal protein intake meets easily. Dietary cysteine can substitute for a portion of the methionine requirement 10Reference 10AnimalThe in vivo sparing of methionine by cysteine in sulfur amino acid requirements in animal models and adult humans — reviewView study →.
- No Upper Limit: none has been established for cysteine or for total sulfur amino acids. That is a data gap, not a safety guarantee.
- Free L-cysteine supplements: uncommon; general-use amounts run from a few hundred mg up to ~1–1.5 g/day. Because free cysteine oxidises readily and can be pro-oxidant at high doses, this is rarely the preferred form.
- NAC — the form most research and practice uses: typically 600–1800 mg/day for antioxidant or mucolytic goals. See N-acetylcysteine.
- L-cystine in hair and skin formulas: ~500 mg/day, usually combined with B-vitamins or
glutathione 6,
7, .8Reference 6RCTSystemic therapy of diffuse effluvium and hair structure damage — randomized controlled trialView study →Reference 7RCTThe efficacy of drug therapy in structural lesions of the hair and in diffuse effluvium — comparative double-blind studyView study →Reference 8RCTThe effects of the oral supplementation of L-cystine associated with reduced L-glutathione-GSH on human skin pigmentation — randomized controlled trialView study → - Timing: amino-acid supplements are usually taken away from a large protein meal to reduce transport competition. There is no established benefit to megadosing above adequacy in well-nourished people.
Safety
At dietary levels and modest supplemental amounts, L-cysteine is generally well tolerated. The specific concern here is not toxicity but chemistry — the free amino acid can do the opposite of what it is taken for.
- Well tolerated at dietary and modest supplemental amounts. GI upset (nausea, cramping) is the dose-limiting effect at higher intakes.
- Free cysteine can be pro-oxidant at high doses. It oxidises readily, which is the main reason NAC and cystine are the preferred delivery forms.
- Higher plasma cysteine tracks with adiposity and cardiometabolic risk in observational data — higher intake should not be assumed beneficial.
- Shares NAC’s interaction cautions. Potential additive vasodilation with nitrates/nitroglycerin, and theoretical interference with chemotherapy regimens that rely on oxidative mechanisms.
- No upper limit is set. No UL exists for cysteine or total sulfur amino acids — a data gap, not evidence of safety.
Full Safety & Interactions Detail
The dose-limiting effect is gastrointestinal upset — nausea, cramping — at higher intakes. The concern specific to the free amino acid is that it oxidises readily and can behave as a pro-oxidant at high concentrations, the opposite of the intended antioxidant effect. This is a major reason NAC and cystine are preferred delivery forms.
Observational data also link higher plasma cysteine to greater adiposity and cardiometabolic risk. That does not establish causation, but it is a reason not to treat more as better.
- Interactions: the free amino acid has few well-characterised drug interactions, but as a glutathione and thiol precursor it shares NAC’s cautions — potential additive effects with nitrates or nitroglycerin (vasodilation) and theoretical interference with some chemotherapy regimens that depend on oxidative mechanisms. Anyone on prescription therapy should clear supplemental doses with a clinician.
Scope disclosure. Interactions were assessed partially — the thiol/NAC-class cautions (nitrates, oxidative chemotherapy) were reviewed; no comprehensive drug-interaction screen was performed for free L-cysteine specifically. Pregnancy and lactation were assessed: dietary cysteine is expected, supplemental-dose safety is not established. No Upper Limit has been set for cysteine or total sulfur amino acids, and that absence is a data gap rather than evidence that any dose is safe. Where cysteine-specific data are missing, that is stated rather than assumed benign.
Dietary intake is expected; avoid concentrated supplements without professional guidance. Cysteine is conditionally essential in the fetus and the preterm infant, and it is transferred maternally, so ordinary dietary cysteine is a normal part of pregnancy nutrition. The safety of supplemental doses above dietary intake in pregnancy and lactation has not been established 11Reference 11ReviewParenteral cysteine supplementation in preterm infants: one size does not fit all — reviewView study →. Do not start free-cysteine or high-dose supplements in pregnancy without medical advice.
References
- Kumar P, et al. (2023). Supplementing glycine and N-acetylcysteine (GlyNAC) in older adults improves glutathione deficiency, oxidative stress, mitochondrial dysfunction, inflammation, physical function, and aging hallmarks — randomized controlled trial. The Journals of Gerontology: Series A. https://pubmed.ncbi.nlm.nih.gov/35975308/
- Sekhar RV (2021). GlyNAC supplementation improves glutathione deficiency, oxidative stress, mitochondrial dysfunction, inflammation, aging hallmarks, metabolic defects, muscle strength, cognitive decline, and body composition — review. The Journal of Nutrition. https://pubmed.ncbi.nlm.nih.gov/34587244/
- Dröge W, Breitkreutz R (2000). Glutathione and immune function — review. Proceedings of the Nutrition Society. https://pubmed.ncbi.nlm.nih.gov/11115795/
- Green CO, et al. (2014). Effects of randomized supplementation of methionine or alanine on cysteine and glutathione production during the early phase of treatment of children with edematous malnutrition — randomized controlled trial. American Journal of Clinical Nutrition. https://pubmed.ncbi.nlm.nih.gov/24598154/
- Lizzo G, et al. (2022). A randomized controlled clinical trial in healthy older adults to determine efficacy of glycine and N-acetylcysteine supplementation on glutathione redox status and oxidative damage — randomized controlled trial. Frontiers in Aging. https://pubmed.ncbi.nlm.nih.gov/35821844/
- Budde J, et al. (1993). Systemic therapy of diffuse effluvium and hair structure damage — randomized controlled trial. Der Hautarzt. https://pubmed.ncbi.nlm.nih.gov/7687592/
- Petri H, et al. (1990). The efficacy of drug therapy in structural lesions of the hair and in diffuse effluvium — comparative double-blind study. Schweizerische Rundschau für Medizin Praxis. https://pubmed.ncbi.nlm.nih.gov/1709511/
- Duperray J, et al. (2022). The effects of the oral supplementation of L-cystine associated with reduced L-glutathione-GSH on human skin pigmentation — randomized controlled trial. Journal of Cosmetic Dermatology. https://pubmed.ncbi.nlm.nih.gov/33834608/
- McGavigan AK, et al. (2015). L-cysteine suppresses ghrelin and reduces appetite in rodents and humans. International Journal of Obesity. https://pubmed.ncbi.nlm.nih.gov/25219528/
- Ball RO, et al. (2006). The in vivo sparing of methionine by cysteine in sulfur amino acid requirements in animal models and adult humans — review. The Journal of Nutrition. https://pubmed.ncbi.nlm.nih.gov/16702340/
- Mohamed I, et al. (2023). Parenteral cysteine supplementation in preterm infants: one size does not fit all — review. Biomedicines. https://pubmed.ncbi.nlm.nih.gov/38255171/
- Chidiac AS, et al. (2023). Paracetamol (acetaminophen) overdose and hepatotoxicity: mechanism, treatment, prevention measures, and estimates of burden of disease — review. Expert Opinion on Drug Metabolism & Toxicology. https://pubmed.ncbi.nlm.nih.gov/37436926/



