
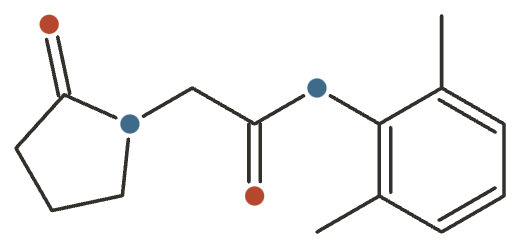
Nefiracetam
A synthetic racetam studied for post-stroke apathy and depression with mixed results — an unapproved investigational drug with documented animal organ toxicity, not a vetted supplement.

Nefiracetam at a Glance
Nefiracetam is a synthetic pyrrolidone (“racetam”) developed in Japan as an investigational cognition-and-mood drug — not as a dietary supplement. Structurally it is piracetam’s scaffold carrying a 2,6-dimethylphenyl group, and it was known in development as DM-9384.
It has no dietary source and no deficiency state to correct; every effect is an extra laid on a normal system.
What makes it unusual is the gap between mechanism and evidence. Nefiracetam’s molecular actions are unusually well mapped — it potentiates NMDA and nicotinic acetylcholine receptors at low nanomolar concentrations through PKC and CaM-kinase signalling — and that deep preclinical literature is exactly what gets quoted in marketing. The human record is far thinner: three double-blind trials, all in stroke patients, with mixed-to-null results, and one Phase 2 Alzheimer’s trial that completed in 2002 and never published a positive result.
The honest bottom line: it was never approved as a medicine anywhere, the one positive human signal is a subgroup at the top dose, and repeat-dose animal toxicology turned up testicular atrophy in two species. For a compound sold online to young men, that last fact is the most decision-relevant thing on the page.
What It’s Used For
Ranked by how well the evidence actually holds up:
- Post-stroke apathy — the best human evidence, and genuinely mixed: one positive double-blind trial at 900 mg/day, one null confirmatory trial that was far too small to settle it.
- Post-stroke depression — a well-conducted trial that was null overall; only the most severely depressed quintile showed anything.
- Cognitive enhancement and dementia — the marketed use, with no published human trial supporting it.
- Neuropathic pain and seizures — rodent models only.
Be sceptical of the memory-enhancement claim that drives online sales. There is no published human trial showing cognitive benefit in healthy people, and the completed Alzheimer’s Phase 2 has no positive result on record. The mechanistic literature is genuinely impressive, but a well-characterised mechanism is not evidence of a benefit — and here the two point in noticeably different directions.
How It Works
Nefiracetam’s mechanism is the strongest part of its file. At low nanomolar concentrations it potentiates NMDA receptor currents by activating protein kinase C, which reduces the voltage-dependent magnesium block that normally gates the receptor 8Reference 8Nefiracetam potentiates NMDA receptor function via protein kinase C activation and reduces magnesium block of the NMDA receptorView study →. In parallel it enhances and prolongs acetylcholine-evoked currents at nicotinic receptors 8Reference 8Nefiracetam potentiates NMDA receptor function via protein kinase C activation and reduces magnesium block of the NMDA receptorView study →. Downstream, it activates CaMKII and related calcium/calmodulin kinases feeding into CREB — the signalling cascade that underwrites long-term potentiation and memory consolidation 9,
The PKC activation follows a bell-shaped dose–response, peaking around 10 nM. That is worth noting because it implies more is not better, and it is a plausible reason the 900 mg and 600 mg arms in the clinical trials behaved so differently.
One correction to a claim that circulates: nefiracetam is sometimes described loosely as “a GABA compound.” Its GABAergic effects are real but secondary — the primary actions are glutamatergic and cholinergic. Describing it as a GABA drug gets the pharmacology backwards.
Pharmacology & Research
Nefiracetam is a synthetic pyrrolidone (“racetam”) nootropic — chemically N-(2,6-dimethylphenyl)-2-(2-oxo-1-pyrrolidinyl)acetamide (CAS 77191-36-7) — developed in Japan as an investigational cognition-and-mood drug rather than a dietary supplement. Its molecular actions are unusually well mapped: at low nanomolar concentrations it potentiates NMDA and nicotinic acetylcholine receptor currents through protein kinase C and CaM-kinase signalling 8,
The clinical reality is much thinner than the mechanism suggests. The only reasonable-sized human trials tested post-stroke apathy and depression, where results were inconsistent and depended on dose and on co-existing depression 1,
Support is an experimental score I’m building — a composite weighted by study type (human > animal > in vitro > review) and study volume. It’s a beta: a fast way to rank strength of evidence at a glance, not a validated metric. Each application links down to its write-up.
This is the compound’s best human evidence, and it is genuinely mixed. In a double-blind trial, 70 stroke patients who had both major depression and apathy were randomised to placebo, 600 mg/day or 900 mg/day nefiracetam; the 900 mg/day group showed significantly greater improvement in Apathy Scale scores than 600 mg/day or placebo over at least 4 weeks 1Reference 1RCTDouble-blind treatment of apathy in patients with poststroke depression using nefiracetam — randomised controlled trialView study →.
A separate, later double-blind, placebo-controlled trial then tested 900 mg/day for 12 weeks in stroke patients with apathy but not depression and found no benefit over placebo — though it randomised only 13 patients, far too few to be conclusive 2Reference 2RCTA randomized, placebo-controlled, double-blind efficacy study of nefiracetam to treat poststroke apathy — randomised controlled trialView study →.
A 2025 PRISMA systematic review of post-stroke apathy treatments concluded nefiracetam “yielded mixed results depending on dose and coexisting depression” 5Reference 5Systematic reviewTreatment of apathy in stroke patients — systematic reviewView study →.
Gap: the one positive result is a subgroup (depressed patients) at the top dose; the confirmatory trial was underpowered, so efficacy in apathy alone is unproven.
In a double-blind trial, 159 patients with major depression within three months of stroke received nefiracetam or placebo. The primary analysis was null — response rates exceeded 70% and remission exceeded 40% in both arms — so nefiracetam was not an effective antidepressant overall. Only the top quintile of baseline Hamilton Depression scores showed a significant effect at 900 mg/day versus 600 mg/day or placebo 3Reference 3RCTDouble-blind randomized treatment of poststroke depression using nefiracetam — randomised controlled trialView study →.
Gap: a well-conducted null result overall; the “most severely depressed” signal is a post-hoc subgroup and should be treated as hypothesis-generating, not evidence of efficacy.
This is the marketed use and the weakest-evidenced. A US Phase 2 trial in mild-to-moderate Alzheimer’s dementia (NCT00001933, n=50) completed in 2002 but has no published positive results on record 4Reference 4Clinical trialNefiracetam therapy of Alzheimer’s type dementia (Phase 2, completed 2002) — clinical trial recordView study →.
The mechanistic case is strong on paper — nefiracetam potentiates NMDA and nicotinic receptors and restores CaMKII/PKC-dependent long-term potentiation and memory in lesioned animals 9Reference 9AnimalNefiracetam activation of CaM kinase II and protein kinase C mediated by NMDA and metabotropic glutamate receptors in olfactory bulbectomized miceView study → — and it reversed synaptic pathology in human MECP2-knockout neurons and organoids, a Rett-syndrome model 11Reference 11Pharmacological reversal of synaptic and network pathology in human MECP2-KO neurons and cortical organoidsView study →.
But none of this is a demonstrated cognitive benefit in healthy people or in a completed, reported dementia trial.
Gap: no published human trial shows memory enhancement; the entire efficacy case for cognition is preclinical or unreported.
In mice, oral, subcutaneous, intrathecal and intracerebroventricular nefiracetam dose-dependently reversed thermal and mechanical hyperalgesia from sciatic-nerve ligation and from streptozotocin-induced diabetes, with no effect in uninjured controls. The analgesia was not blocked by the opioid antagonist naloxone but was blocked by the nicotinic antagonist mecamylamine, indicating a non-opioid, nicotinic-cholinergic and neuropathy-specific mechanism 12Reference 12AnimalNonopioid and neuropathy-specific analgesic action of the nootropic drug nefiracetam in miceView study →.
Gap: entirely a rodent model; no human trials for pain of any kind.
In a rat model of post-ischemic non-convulsive seizures, intravenous nefiracetam reduced seizure frequency and duration and protected cultured neurons against veratridine and glutamate toxicity, implicating sodium-channel modulation 13Reference 13AnimalNefiracetam attenuates post-ischemic nonconvulsive seizures in rats and protects neuronal cell death induced by veratridine and glutamateView study →; related rodent work shows anticonvulsant activity in kindling and kainic-acid models and attenuation of pro-inflammatory cytokines and GABA transporters in ischemic brain 13Reference 13AnimalNefiracetam attenuates post-ischemic nonconvulsive seizures in rats and protects neuronal cell death induced by veratridine and glutamateView study →.
Gap: preclinical only, and paradoxically nefiracetam has also shown proconvulsant/excitatory actions at some doses — it is not an anticonvulsant drug in people.
Mechanisms
| Target / pathway | Effect | Relevant to |
|---|---|---|
| NMDA receptor (glycine site) | Potentiates currents; reduces voltage-dependent Mg²⁺ block via PKC 8Reference 8Nefiracetam potentiates NMDA receptor function via protein kinase C activation and reduces magnesium block of the NMDA receptorView study → | Cognitionseizurespain |
| Nicotinic acetylcholine receptors | Enhances/prolongs ACh-evoked currents 8Reference 8Nefiracetam potentiates NMDA receptor function via protein kinase C activation and reduces magnesium block of the NMDA receptorView study → | Cognitiondementia |
| Protein kinase C (PKCα) | Activated (bell-shaped, peak ~10 nM); phosphorylates NMDA receptor 8Reference 8Nefiracetam potentiates NMDA receptor function via protein kinase C activation and reduces magnesium block of the NMDA receptorView study → | CognitionLTP |
| CaMKII / CaMKI / CaMKIV → CREB | Activated; restores LTP and phosphorylation in lesioned brain 9, | Memorymood |
| Intracellular Ca²⁺ and cAMP | Increased; sustained Ca²⁺ current 17Reference 17General pharmacological profile of the new cognition-enhancing agent nefiracetamView study → | Neurotransmitter release |
| GABAergic signalling / GABA transporters | Modulated (secondary, not the primary action); normalises GAT-1/GAT-3 in ischemic brain | Seizuresmood |
Pharmacokinetics
Nefiracetam is absorbed rapidly and almost completely after oral dosing in healthy volunteers, reaching peak serum levels within about 1.5–2 hours and showing linear (dose-proportional) kinetics from 10–200 mg 6,
Clinical trials
Human trial activity is sparse and largely historical: three published double-blind RCTs (post-stroke depression and apathy) and one completed but unreported Phase 2 Alzheimer’s trial (NCT00001933). It is an off-patent investigational drug with essentially no current industry trial activity, and animal toxicity findings (below) discouraged further development in some programs.
| Completed | Planned | Terminated | Preclinical |
|---|---|---|---|
| ~4 | 0 | 0 | ~100+ |
Last checked: August 2026.
Dietary Sources
Nefiracetam has no dietary source — it is a fully synthetic pyrrolidone drug, not a nutrient found in food. There is no “natural” nefiracetam to eat and no deficiency state to correct.
How it’s made: it is manufactured synthetically from a 2-oxopyrrolidinyl-acetamide scaffold coupled to a 2,6-dimethylaniline group (the structural feature that distinguishes it from piracetam). It exists in several solid-state forms (a monohydrate and two anhydrate polymorphs) that differ in dissolution and solubility, which matters for formulation rather than for the consumer.
Dosage
There is no established supplement dose and no reference intake — nefiracetam is not a nutrient, so no RDA/AI or Tolerable Upper Intake Level exists. The only human doses on record come from clinical research:
| Context | Dose studied | Notes |
|---|---|---|
| Post-stroke apathy / depression RCTs | 600 or 900 mg/day | The 900 mg/day arm carried the only positive signal; both under medical supervision 1, |
| Alzheimer’s Phase 2 (NCT00001933) | investigational | No published positive result 4Reference 4Clinical trialNefiracetam therapy of Alzheimer’s type dementia (Phase 2, completed 2002) — clinical trial recordView study → |
| Healthy-volunteer PK studies | 10–200 mg single; 200 mg ×3/day | Used to characterise kinetics, not efficacy 6Reference 6Single- and multiple-dose pharmacokinetics of nefiracetam in healthy volunteersView study → |
These are research protocol doses, not personal recommendations. Absorption is rapid and nearly complete; food delays but does not reduce absorption, so timing with meals is not critical for exposure 6Reference 6Single- and multiple-dose pharmacokinetics of nefiracetam in healthy volunteersView study →. Because CYP3A4 forms its main oxidative metabolite in laboratory tests, the practical caution is drug-interaction risk rather than a defined ceiling.
Safety
Nefiracetam’s safety profile is the decision-relevant part, and it is not reassuring for casual use.
- Never approved as a medicine or a supplement, anywhere. There is no regulated human safety dossier for over-the-counter exposure.
- Testicular toxicity in two species. High oral doses caused seminiferous-tubule atrophy, falling testosterone and malformed sperm in dogs and rats — a real concern for a compound marketed to young men.
- Renal papillary necrosis in dogs at 300 mg/kg/day, tied to a dog-specific metabolite. Human relevance uncertain, but it flagged the compound during development.
- CYP3A4 interactions are plausible. CYP3A4 forms its main oxidative metabolite in laboratory tests, so strong inhibitors could raise exposure and inducers lower it. None of this has been studied in people.
- CNS-depressant effects in animals — ataxia, reduced locomotion, potentiated anaesthesia, transient falls in blood pressure at higher doses.
- No upper limit is set. It is not a nutrient; the highest studied human dose is 900 mg/day under supervision.
Full Safety & Interactions Detail
It is an unapproved investigational drug, never cleared as a medicine or a dietary supplement anywhere, so there is no regulated human safety dossier for OTC exposure. Its general pharmacology in animals includes CNS-depressant effects (ataxia, reduced locomotion, potentiation of anaesthesia) and transient falls in blood pressure at higher doses 17Reference 17General pharmacological profile of the new cognition-enhancing agent nefiracetamView study →.
The most serious signals come from repeat-dose animal toxicology:
- Testicular toxicity. In beagle dogs, high oral doses (180–300 mg/kg/day) lowered testicular and serum testosterone after a single dose and produced seminiferous-tubule atrophy, reduced sperm motility and malformed sperm after 4 weeks 14Reference 14Testicular toxicity induced in dogs by nefiracetam, a neurotransmission enhancerView study →. Rats showed the same pattern (spermatid/spermatocyte degeneration, falling testosterone) at 1500 mg/kg/day 15Reference 15AnimalInvestigation of testicular toxicity of nefiracetam, a neurotransmission enhancer, in ratsView study →. These doses are far above human exposures, but the mechanism — impaired Leydig-cell testosterone synthesis — is a genuine concern for a compound sold to young men.
- Renal papillary necrosis. This was dog-specific — not seen in rats or monkeys — at 300 mg/kg/day, and appears tied to a dog-specific metabolite (M-18) and low baseline renal prostaglandin synthesis 16Reference 16Comprehensive evaluation of canine renal papillary necrosis induced by nefiracetam, a neurotransmission enhancerView study →. Human relevance is uncertain but it flagged the compound for close monitoring.
Drug interactions: in human liver microsomes, nefiracetam’s 5-hydroxylation is carried out chiefly by CYP3A4, with a minor CYP1A2 share 18Reference 18Nefiracetam metabolism by human liver microsomes: role of cytochrome P450 3A4 and cytochrome P450 1A2 in 5-hydroxynefiracetam formationView study →. On that basis, strong CYP3A4 inhibitors (ketoconazole, clarithromycin, ritonavir, grapefruit) might raise exposure and inducers (rifampicin, carbamazepine, St John’s wort) might lower it. Additive CNS depression with sedatives or alcohol is plausible from its animal profile. None of this has been formally studied in people taking it as a supplement.
Scope disclosure. Interactions assessed? Partially — CYP3A4/1A2 metabolism is documented in human liver microsomes, predicting the interactions above, but no dedicated human interaction trials exist. Pregnancy/lactation assessed? No human data, and animal reproductive toxicity is documented. Upper limit established? No — and absence of a UL does not imply any amount is safe. Nefiracetam’s long-term human safety is simply unknown; the animal toxicology is a caution, not a clean bill.
Avoid. There are no human pregnancy or lactation safety data, and this is an unapproved drug with demonstrated animal reproductive (testicular) toxicity. It should not be used in pregnancy, when trying to conceive, or while breastfeeding.
Related racetams: piracetam, aniracetam, oxiracetam, pramiracetam, phenylpiracetam, coluracetam and fasoracetam.
References
- Robinson RG, Jorge RE, Clarence-Smith K, Starkstein S. (2009). Double-blind treatment of apathy in patients with poststroke depression using nefiracetam — randomised controlled trial. The Journal of Neuropsychiatry and Clinical Neurosciences. https://pubmed.ncbi.nlm.nih.gov/19622685/
- Starkstein SE, Brockman S, Hatch KK, et al. (2016). A randomized, placebo-controlled, double-blind efficacy study of nefiracetam to treat poststroke apathy — randomised controlled trial. Journal of Stroke and Cerebrovascular Diseases. https://pubmed.ncbi.nlm.nih.gov/26915605/
- Robinson RG, Jorge RE, Clarence-Smith K. (2008). Double-blind randomized treatment of poststroke depression using nefiracetam — randomised controlled trial. The Journal of Neuropsychiatry and Clinical Neurosciences. https://pubmed.ncbi.nlm.nih.gov/18451188/
- National Institute of Mental Health. Nefiracetam therapy of Alzheimer’s type dementia (Phase 2, completed 2002) — clinical trial record. ClinicalTrials.gov. https://clinicaltrials.gov/study/NCT00001933
- Ruiz-Franco ML, Amaya-Pascasio L, Gil-Rodríguez M, et al. (2025). Treatment of apathy in stroke patients — systematic review. Frontiers in Neurology. https://pubmed.ncbi.nlm.nih.gov/41383225/
- Fujimaki M, et al. (1992). Single- and multiple-dose pharmacokinetics of nefiracetam in healthy volunteers. The Journal of Pharmacy and Pharmacology. https://pubmed.ncbi.nlm.nih.gov/1360528/
- Fujimaki Y, Sudo K, Hakusui H (1993). Pharmacokinetics of nefiracetam and three metabolites in humans and stereoselective hydroxylation of its pyrrolidine ring. Xenobiotica. https://pubmed.ncbi.nlm.nih.gov/8484264/
- Moriguchi S, Shioda N, Maejima H, et al. (2007). Nefiracetam potentiates NMDA receptor function via protein kinase C activation and reduces magnesium block of the NMDA receptor. Molecular Pharmacology. https://pubmed.ncbi.nlm.nih.gov/17095583/
- Moriguchi S, et al. (2009). Nefiracetam activation of CaM kinase II and protein kinase C mediated by NMDA and metabotropic glutamate receptors in olfactory bulbectomized mice. Journal of Neurochemistry. https://pubmed.ncbi.nlm.nih.gov/19457128/
- Han F, Nakano T, Yamamoto Y, et al. (2009). Improvement of depressive behaviors by nefiracetam is associated with activation of CaM kinases in olfactory bulbectomized mice. Brain Research. https://pubmed.ncbi.nlm.nih.gov/19233146/
- Trujillo CA, et al. (2021). Pharmacological reversal of synaptic and network pathology in human MECP2-KO neurons and cortical organoids. EMBO Molecular Medicine. https://pubmed.ncbi.nlm.nih.gov/33501759/
- Rashid MH, Ueda H (2002). Nonopioid and neuropathy-specific analgesic action of the nootropic drug nefiracetam in mice. The Journal of Pharmacology and Experimental Therapeutics. https://pubmed.ncbi.nlm.nih.gov/12235255/
- Lu XC, Dave JR, Chen Z, et al. (2013). Nefiracetam attenuates post-ischemic nonconvulsive seizures in rats and protects neuronal cell death induced by veratridine and glutamate. Life Sciences. https://pubmed.ncbi.nlm.nih.gov/23603142/
- Shimomura K, Shimada M, Hagiwara M, et al. (2004). Testicular toxicity induced in dogs by nefiracetam, a neurotransmission enhancer. Reproductive Toxicology. https://pubmed.ncbi.nlm.nih.gov/15082078/
- Shimada M, Shikanai Y, Shimomura K, et al. (2003). Investigation of testicular toxicity of nefiracetam, a neurotransmission enhancer, in rats. Toxicology Letters. https://pubmed.ncbi.nlm.nih.gov/12849691/
- Tsuchiya Y, Takahashi Y, Jindo T, et al. (2003). Comprehensive evaluation of canine renal papillary necrosis induced by nefiracetam, a neurotransmission enhancer. European Journal of Pharmacology. https://pubmed.ncbi.nlm.nih.gov/12954368/
- Kitano Y, Makino M, Usui C, et al. (1994). General pharmacological profile of the new cognition-enhancing agent nefiracetam. Arzneimittel-Forschung. https://pubmed.ncbi.nlm.nih.gov/8018090/
- Fujimaki Y, Arai N, Nakazawa T, et al. (2001). Nefiracetam metabolism by human liver microsomes: role of cytochrome P450 3A4 and cytochrome P450 1A2 in 5-hydroxynefiracetam formation. The Journal of Pharmacy and Pharmacology. https://pubmed.ncbi.nlm.nih.gov/11428655/
For half-lives, timing and stacking across the nootropics on this site, see the Nootropic Dosage Guide.



