
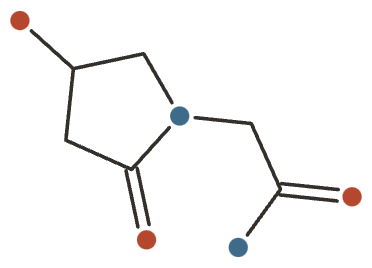

Oxiracetam at a Glance
Oxiracetam is a synthetic racetam — a water-soluble relative of piracetam, dosed in the high hundreds of milligrams to a gram or two.
It is the “stimulating” member of the family, and its clinical work has focused on cognitive recovery after brain injury and in vascular cognitive impairment, where it was used as a medicine in Italy and elsewhere from the 1980s.
What It’s Used For
- Traumatic brain injury recovery — supports cognitive recovery after head injury.
- Vascular cognitive impairment — improves cognition where blood supply is the cause.
- Dementia & degenerative decline — used in degenerative cognitive decline.
- Healthy cognitive enhancement — the popular use, for memory and focus.
How It Works
Oxiracetam positively modulates AMPA and NMDA receptors, facilitating long-term potentiation — the synaptic process behind memory consolidation, and the mechanistic signature the racetam family shares. It also increases high-affinity choline uptake and acetylcholine turnover, which is why racetams are traditionally paired with a choline source.
It is water-soluble and short-acting, so it is split across the day rather than taken once, and usually dosed earlier because it is mildly stimulating.
The full trial record is in Pharmacology & Research below.
Pharmacology & Research
Oxiracetam is a synthetic, water-soluble racetam — a structural derivative of piracetam built on the same 2-pyrrolidinone ring — developed in the 1970s–80s (as ISF-2522 / CGP 21690E) and studied almost entirely as a treatment for impaired cognition rather than enhancement in healthy people. That distinction is the key to reading its evidence: the compound has a real, if modest, signal in acquired cognitive injury — a large modern phase 3 trial found it improved cognition after traumatic brain injury 1Reference 1RCTSignal Transduction and Targeted TherapyView study → — but the most rigorous prevention trial in post-stroke patients was flatly negative — a result whose authors note supports South Korea’s regulatory decision to suspend its use 2Reference 2RCTOxiracetam and physical activity in preventing cognitive decline after stroke: a multicenter, randomized controlled trial (2026) — [randomised controlled trial]. European Stroke Journal. https://pubmed.ncbi.nlm.nih.gov/41614470/View study →.
The popular use as a general “study aid” in healthy adults rests on almost no direct evidence. Pharmacologically it is unusual for a nootropic in being barely metabolized — the great majority is excreted unchanged by the kidneys — so renal function, not liver metabolism, governs its clearance 3,
Support is an experimental score I’m building — a composite weighted by study type (human > animal > in vitro > review) and study volume. It’s a beta: a fast way to rank strength of evidence at a glance, not a validated metric. Each application links down to its write-up.
The strongest single piece of evidence. A 2025 multicenter, double-blind, randomized phase 3 trial in China enrolled 590 patients with mild-to-moderate TBI (Glasgow Coma Scale 10–15) and randomized them 2:2:1 to L-oxiracetam 4 g/day, racemic oxiracetam 6 g/day, or placebo for 90 days 1Reference 1RCTSignal Transduction and Targeted TherapyView study →.
On the primary cognitive endpoint (LOTCA), both active arms beat placebo; L-oxiracetam showed a mean advantage of ~9 points over placebo (Cohen’s d = 0.48, a moderate effect) and was modestly better than the racemate 1Reference 1RCTSignal Transduction and Targeted TherapyView study →.
Serious adverse events did not differ between groups 1Reference 1RCTSignal Transduction and Targeted TherapyView study →.
Note the caveats: doses are far higher (4–6 g/day) than the 750–1,600 mg/day sold as a supplement, the trial was single-country, and there was meaningful loss to follow-up.
Gap: A single (albeit large) positive trial at high dose in one country; not yet independently replicated, and the supplement dose is a fraction of what was tested.
The largest body of oxiracetam data is in vascular/multi-infarct cognitive impairment, but it is uneven. Older double-blind trials from the 1980s–90s reported benefits on scales such as the IPSC-E, Blessed Dementia Scale and MMSE in mixed degenerative/multi-infarct dementia 6,
In modern practice (mainly China), it is often used adjunctively — a 120-patient trial found nicergoline plus oxiracetam improved MoCA more than nicergoline alone 5Reference 5RCTClinical efficacy and safety of nicergoline combined with oxiracetam in the treatment of vascular cognitive impairment (2020) — [randomised controlled trial]. Pakistan Journal of Pharmaceutical Sciences. https://pubmed.ncbi.nlm.nih.gov/32173636/View study →.
A 2024 Bayesian network meta-analysis of 194 vascular-dementia RCTs placed oxiracetam among the drugs with a favorable safety profile, but not among the most effective 10Reference 10Meta-analysisPharmacological treatments for vascular dementia: a systematic review and Bayesian network meta-analysis (2024) — [systematic review / meta-analysis]. Frontiers in Pharmacology. https://pubmed.ncbi.nlm.nih.gov/39239652/View study →.
Critically, the best modern trial — a 500-patient Korean RCT testing whether oxiracetam could prevent post-stroke cognitive impairment — found no difference from placebo on MMSE or CDR-SB over 36 weeks 2Reference 2RCTOxiracetam and physical activity in preventing cognitive decline after stroke: a multicenter, randomized controlled trial (2026) — [randomised controlled trial]. European Stroke Journal. https://pubmed.ncbi.nlm.nih.gov/41614470/View study →.
Gap: Treatment-of-established-impairment trials are old and mostly positive; the one rigorous modern prevention trial was null, so the benefit may be confined to already-impaired patients.
Results split sharply by dementia type and trial rigor. Several older placebo-controlled trials in mild-to-moderate primary degenerative or mixed dementia reported improvements on MMSE, attention and instrumental activities of daily living at 1,600 mg/day 7,
But in the disease people most associate with dementia — Alzheimer’s — a carefully conducted double-blind trial found oxiracetam produced no improvement on any neuropsychological measure and concluded it was “ineffective in reducing cognitive impairment due to Alzheimer’s disease” 8Reference 8Clinical trialTreatment trial of oxiracetam in Alzheimer’s disease (1992) — [clinical trial, negative]. Archives of Neurology. https://pubmed.ncbi.nlm.nih.gov/1444879/View study →.
Gap: The positive signals are in heterogeneous, loosely defined “degenerative dementia” from decades-old trials; the cleaner Alzheimer’s trial was negative.
This is what most supplement buyers actually want, and it is the weakest-evidenced use. There is no published RCT showing oxiracetam improves real-world cognition in healthy, non-impaired adults. The nearest human data is a “scopolamine model of amnesia” study in 12 healthy volunteers: an acute 1,600 mg dose partly reversed the memory impairment induced by scopolamine, and showed dose-related antagonism of that chemical deficit 7Reference 7RCTEffects of acute doses of oxiracetam in the scopolamine model of human amnesia (1993) — [randomised controlled trial]. Psychopharmacology. https://pubmed.ncbi.nlm.nih.gov/7870912/View study →.
That is a pharmacodynamic challenge model — evidence the drug engages memory pathways — not evidence it makes an unimpaired brain perform better.
Gap: Benefit in healthy users is inferred from a deficit-reversal model, not demonstrated; the everyday “focus and logical thinking” claim is essentially untested in trials.
Mechanisms
| Target / pathway | Effect | Relevant to |
|---|---|---|
| Cholinergic signaling | Increases high-affinity choline uptake and acetylcholine turnover | Memorylearning; rationale for pairing with a choline source |
| Glutamatergic AMPA/NMDA receptors | Positive modulation; facilitates long-term potentiation | Memory consolidationTBI/VCI recovery |
| Membrane phospholipid / PKC signaling | Modulation (preclinical) | Proposed neuroprotection |
| Cerebral energy metabolism | Enhanced glucose/ATP utilization (older preclinical claims) | Age-related and vascular cognitive decline |
Pharmacokinetics
Oxiracetam is absorbed rapidly after oral dosing, with peak plasma levels at roughly 1–2 hours 4,
Clinical trials
Oxiracetam is off-patent and decades old, so there is little Western pharmaceutical trial activity — Western registries list essentially one recent study, while contemporary trials are registered on Chinese and Korean registries. The two largest modern trials (a positive phase 3 in TBI and a null prevention trial in post-stroke patients) were both conducted in East Asia.
| Completed | Planned | Terminated | Preclinical |
|---|---|---|---|
| ~20+(mostly 1980s–90s + 3 modern) | 0–1 | 0 | Many(rodent/dog) |
Last checked: July 2026.
Intake & Dosage
Because oxiracetam is not a nutrient, there is no RDA, no AI, and no Tolerable Upper Intake Level — the concept of correcting a deficiency does not apply. The doses to reference are those studied in research, not a personal recommendation.
- Common supplement range: 750–1,600 mg/day, typically split into 2–3 doses 6–8 hours apart. The short (~3–6 h) half-life is the reason for split dosing 4Reference 4Oxiracetam pharmacokinetics following single and multiple dose administration in the elderly (1987) — [pharmacokinetics]. European Journal of Drug Metabolism and Pharmacokinetics. https://pubmed.ncbi.nlm.nih.gov/3691580/View study →.
- Research doses run much higher: the modern TBI phase 3 trial used 6 g/day of racemic oxiracetam (4 g/day of the L-enantiomer), and vascular-impairment trials commonly used 1,600 mg/day 1,
6Reference 1RCTSignal Transduction and Targeted TherapyView study →Reference 6RCTOxiracetam in the treatment of primary degenerative and multi-infarct dementia: a double-blind, placebo-controlled study (1989) — [randomised controlled trial]. Neuropsychobiology. https://pubmed.ncbi.nlm.nih.gov/2693996/View study → . - Renal impairment: clearance is almost entirely renal, and half-life lengthens dramatically as kidney function falls — doses should be reduced in kidney disease 3,
11Reference 3AnimalAbsorption and disposition of 14C-labelled oxiracetam in rat, dog and manView study →Reference 11Clinical trialPharmacokinetics of oxiracetam in patients with renal impairment after a 800 mg single oral dose (1990) — [pharmacokinetics]. European Journal of Drug Metabolism and Pharmacokinetics. https://pubmed.ncbi.nlm.nih.gov/2253654/View study → . - Enzyme-inducing antiepileptics (carbamazepine, valproate) shorten its half-life, so more frequent dosing may be needed in those patients 13Reference 13Pilot study to determine the interaction of oxiracetam with antiepileptic drugs (1990) — [pharmacokinetics]. Clinical Pharmacokinetics. https://pubmed.ncbi.nlm.nih.gov/2108837/View study →.
- With food / choline: many users pair it with a choline donor to offset racetam-associated headache; this is a practical convention, not a trial-validated protocol.
These are doses studied in research, not a personal recommendation.
Safety
Oxiracetam’s trial record is mild — headache is the usual complaint — so the things worth actually knowing are how it is cleared and what it is taken with: kidneys do nearly all the work, and two common antiepileptics change its kinetics.
- Generally well tolerated. Adverse events were mild, dose-independent, and often no more frequent than placebo, with no excess of serious events in the large TBI trial.
- Avoid in pregnancy and breastfeeding. No safety data at all — see the box below.
- Renal impairment raises exposure and prolongs the half-life several-fold. A dose reduction is warranted.
- Carbamazepine and valproate shorten its half-life. Not contraindicated, but dosing frequency may need adjusting.
- Headache is the common complaint. It is the reason for the choline-pairing convention; restlessness or insomnia can follow a late dose.
- Not an approved drug or supplement in the US, and suspended in South Korea. A genuine regulatory caveat, not a formality.
Full Safety & Interactions Detail
Across the trial record oxiracetam has been generally well tolerated, with adverse events that were mild, dose-independent, and often no more frequent than placebo 1,
The most commonly reported issues are headache (the reason for the choline-pairing convention), mild gastrointestinal upset (loose stools were the main finding in canine toxicology), and — consistent with its mildly stimulating quality — occasional restlessness, agitation or insomnia if taken late in the day. Serious adverse events were not elevated versus placebo in the large modern TBI trial 1Reference 1RCTSignal Transduction and Targeted TherapyView study →.
Two safety points deserve emphasis. First, oxiracetam is cleared almost entirely by the kidneys, so renal impairment both raises exposure and prolongs the half-life several-fold — a dose reduction is warranted 3,
Second, it has a documented pharmacokinetic interaction with the antiepileptics carbamazepine and valproate, which shorten its half-life; the interaction did not appear to change antiepileptic drug levels, and concurrent use was not judged contraindicated, but dosing frequency may need adjustment 13Reference 13Pilot study to determine the interaction of oxiracetam with antiepileptic drugs (1990) — [pharmacokinetics]. Clinical Pharmacokinetics. https://pubmed.ncbi.nlm.nih.gov/2108837/View study →.
Regulatory status is a genuine caveat, not a formality: oxiracetam is not approved as a drug or dietary supplement in the United States, and its use is subject to a regulatory suspension in South Korea — a decision the authors of a 500-patient trial (which found no benefit for preventing post-stroke cognitive decline) say their findings support 2Reference 2RCTOxiracetam and physical activity in preventing cognitive decline after stroke: a multicenter, randomized controlled trial (2026) — [randomised controlled trial]. European Stroke Journal. https://pubmed.ncbi.nlm.nih.gov/41614470/View study →.
Verdict: avoid. There are no human pregnancy or lactation safety data for oxiracetam, and no basis to establish safety. In the absence of any studies, it should not be used during pregnancy or breastfeeding.
References
- Efficacy and safety of L-oxiracetam on cognitive function in patients with traumatic brain injury: a multicentre, randomised, double-blind, phase 3 clinical trial (Year 2025) — [randomised controlled trial]. Signal Transduction and Targeted Therapy. https://pubmed.ncbi.nlm.nih.gov/41381424/
- Oxiracetam and physical activity in preventing cognitive decline after stroke: a multicenter, randomized controlled trial (2026) — [randomised controlled trial]. European Stroke Journal. https://pubmed.ncbi.nlm.nih.gov/41614470/
- Gschwind HP, Schütz H, Wigger N, et al. (1992). Absorption and disposition of 14C-labelled oxiracetam in rat, dog and man. Eur J Drug Metab Pharmacokinet. https://pubmed.ncbi.nlm.nih.gov/1499599/
- Oxiracetam pharmacokinetics following single and multiple dose administration in the elderly (1987) — [pharmacokinetics]. European Journal of Drug Metabolism and Pharmacokinetics. https://pubmed.ncbi.nlm.nih.gov/3691580/
- Clinical efficacy and safety of nicergoline combined with oxiracetam in the treatment of vascular cognitive impairment (2020) — [randomised controlled trial]. Pakistan Journal of Pharmaceutical Sciences. https://pubmed.ncbi.nlm.nih.gov/32173636/
- Oxiracetam in the treatment of primary degenerative and multi-infarct dementia: a double-blind, placebo-controlled study (1989) — [randomised controlled trial]. Neuropsychobiology. https://pubmed.ncbi.nlm.nih.gov/2693996/
- Effects of acute doses of oxiracetam in the scopolamine model of human amnesia (1993) — [randomised controlled trial]. Psychopharmacology. https://pubmed.ncbi.nlm.nih.gov/7870912/
- Treatment trial of oxiracetam in Alzheimer’s disease (1992) — [clinical trial, negative]. Archives of Neurology. https://pubmed.ncbi.nlm.nih.gov/1444879/
- Oxiracetam in dementia: a double-blind, placebo-controlled study (1992) — [randomised controlled trial]. Acta Neurologica Scandinavica. https://pubmed.ncbi.nlm.nih.gov/1414239/
- Pharmacological treatments for vascular dementia: a systematic review and Bayesian network meta-analysis (2024) — [systematic review / meta-analysis]. Frontiers in Pharmacology. https://pubmed.ncbi.nlm.nih.gov/39239652/
- Pharmacokinetics of oxiracetam in patients with renal impairment after a 800 mg single oral dose (1990) — [pharmacokinetics]. European Journal of Drug Metabolism and Pharmacokinetics. https://pubmed.ncbi.nlm.nih.gov/2253654/
- Pharmacokinetics of oxiracetam following intravenous and oral administration in healthy volunteers (1984) — [pharmacokinetics]. European Journal of Drug Metabolism and Pharmacokinetics. https://pubmed.ncbi.nlm.nih.gov/6519128/
- Pilot study to determine the interaction of oxiracetam with antiepileptic drugs (1990) — [pharmacokinetics]. Clinical Pharmacokinetics. https://pubmed.ncbi.nlm.nih.gov/2108837/
- Safety, tolerability, and pharmacokinetics of oral (S)-oxiracetam in Chinese healthy volunteers: a randomized, double-blind, controlled phase I study (2024) — [randomised controlled trial]. European Journal of Pharmaceutical Sciences. https://pubmed.ncbi.nlm.nih.gov/37898393/
For half-lives, timing and stacking across the nootropics on this site, see the Nootropic Dosage Guide.



