
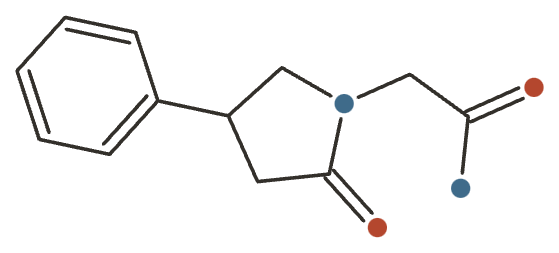

Phenylpiracetam at a Glance
Phenylpiracetam is a racetam — a piracetam molecule with a phenyl group added to the pyrrolidinone ring — developed in the Soviet Union and sold as carphedon, phenotropil and fonturacetam. That single structural change makes it pharmacologically distinct from its parent: it acts as a selective dopamine-transporter (DAT) inhibitor, which is why it feels stimulating in a way plain piracetam does not, and why it works at milligram rather than gram doses.
It is wholly synthetic, with no dietary or natural source. Everything sold is manufactured — a fact that matters more here than for most compounds here, because market surveillance repeatedly finds products under this name that are mislabelled, misdosed or adulterated with other unapproved drugs.
Pharmacologically, this is a drug with a real but lopsided clinical record, not a nutrient. There is no deficiency to correct; every effect is an extra laid on a normal system. Almost the entire human evidence base is Russian or post-Soviet, much of it open-label or single-sponsor, and there are essentially no registered Western trials.
The honest bottom line: the best human data are for mental fatigue and post-stroke recovery in clinical populations. The effect most Western buyers want — sharper focus and stamina in an already-healthy brain — is close to unstudied, and the practical risks are regulatory and quality-control rather than pharmacological.
What It’s Used For
Ranked by how well the evidence actually holds up:
- Asthenia and mental fatigue — the strongest human signal, from a 549-patient meta-analysis and a 1,170-patient observational program. All Russian, all on a self-report fatigue scale.
- Stroke rehabilitation — one 400-patient controlled trial showing better functional recovery, supported by animal neuroprotection data. Never replicated outside Russia.
- Chronic cerebral ischaemia — comparative and observational data that overlap heavily with the fatigue signal.
- Epilepsy (adjunct) — a genuine anticonvulsant action plus a small double-blind placebo-controlled add-on trial. Adjunct only; monotherapy is untested.
- Cognitive enhancement in healthy people — the reason most people buy it, and the weakest-evidenced use on the page.
- Physical stamina — inferred from its stimulant pharmacology and its doping ban, not from any controlled trial.
Be sceptical of the two claims that sell the product: “focus” and “endurance.” Both are extrapolated from clinically impaired populations and animal models. The animal work is pointed about this — nootropic effects track a rise in hippocampal BDNF that appears only under conditions of cognitive deficiency, not in healthy high-performers 22Reference 22AnimalEffects of nootropic drugs on hippocampal and cortical BDNF levels in mice — animal studyView study →. Benefits after brain injury or in a fatigue state are poor evidence for boosting a brain that is already working well. Add rapid tolerance to the stimulant effect, and the everyday use case is weaker than the reputation suggests.
How It Works
The phenyl group does two things. It makes the molecule more lipophilic, so it crosses the blood–brain barrier far more readily than piracetam — the reason doses are measured in milligrams rather than grams. And it confers selective dopamine-transporter inhibition: phenylpiracetam blocks dopamine reuptake without meaningful noradrenaline or serotonin activity, raising synaptic dopamine. That is the mechanistic basis for the alerting, motivating “stimulant feel,” for the ergogenic reputation, and for the WADA ban.
A second property has no counterpart in piracetam: a genuine anticonvulsant action, identified in the original 1983 characterisation of the molecule 15Reference 15Pharmacological characteristics of a new phenyl analog of piracetam — 4-phenylpiracetam — animal studyView study →. This is what makes the adjunctive epilepsy work mechanistically coherent rather than opportunistic — most nootropics tend to lower seizure threshold.
The two enantiomers are not interchangeable, which matters because the marketed product is a racemate. The R-enantiomer carries most of the memory-enhancing activity, while both contribute to locomotor activation — so half of what you swallow is memory-inactive 11Reference 11Investigation into stereoselective pharmacological activity of phenotropil — comparative animal studyView study →. The S-enantiomer has its own separate rodent effects on body weight, glucose and leptin 13Reference 13S-phenylpiracetam, a selective DAT inhibitor, reduces body weight gain without influencing locomotor activity — animal studyView study →.
Tolerance to the stimulant component develops quickly, which is consistently reported and mechanistically expected of a dopaminergic agent. It is the main practical limit on daily use.
Pharmacology & Research
Phenylpiracetam is a synthetic racetam — a piracetam molecule with a phenyl group added to the pyrrolidone ring — developed in the Soviet Union and sold under the names carphedon, phenotropil and fonturacetam. The phenyl substitution gives it a psychostimulant character that plain piracetam lacks: it acts as a selective dopamine-transporter (DAT) inhibitor, which is the mechanistic basis for its “energizing” reputation and for its ban in sport. The evidence posture is unusual. Almost the entire human clinical base is Russian/post-Soviet, much of it open-label, weakly controlled or single-sponsor, and hard to independently verify — there are essentially no registered Western trials (ClinicalTrials.gov returns zero). Because it is not an approved supplement or medicine in most Western countries, it is also frequently adulterated or mislabelled in the products that carry its name, so what is in the bottle is a bigger practical question than for most nutraceuticals.
Support is an experimental score I’m building — a composite weighted by study type (human > animal > in vitro > review) and study volume. It’s a beta: a fast way to rank strength of evidence at a glance, not a validated metric. Each application links down to its write-up. Every score here is tempered downward for the same reason: the human literature is almost entirely Russian, open-label-heavy, and not independently replicated in the West.
This is the strongest human signal. A 2025 systematic review and meta-analysis pooled 11 studies and 549 patients (mean age 45.9) taking 200 mg/day for one month, and found asthenia on the MFI-20 scale fell by an average of 16.3 points (95% CI 8.85–23.85) 2Reference 2Meta-analysisEfficacy and safety of fonturacetam in asthenia: a systematic review and meta-analysisView study →.
A separate non-interventional observational program (TRIUMPH) followed 1,170 patients with chronic brain ischaemia on 100 mg/day and reported a >2-fold reduction in asthenia severity by three months, with younger patients responding faster 3Reference 3Clinical trialTreatment of asthenic syndrome in patients with chronic brain ischemia: results of the non-interventional observational program TRIUMPH — observational studyView study →.
The effect is consistent across the Russian literature and is echoed in the drug’s own review articles 4Reference 4ReviewPharmacological effects of fonturacetam (Actitropil) and prospects for its clinical use — reviewView study →.
The honest limits: every trial is Russian, MFI-20 is a self-report scale, the pooled studies are heavily open-label, and the meta-analysis and much of the primary work centre on a single branded product (Actitropil/fonturacetam), so publication and sponsorship bias cannot be ruled out.
Gap: No independent, blinded, non-Russian replication; the outcome is a subjective fatigue scale rather than an objective performance measure.
A controlled study of 400 ischaemic-stroke patients gave 200 of them 400 mg/day of phenotropil across three courses during the year after stroke; recovery of neurological function and daily-living activity (Barthel, Lindmark, Scandinavian and Merton–Sutton scales) was significantly better than controls (p < 0.0001) 5Reference 5Clinical trialEfficacy of phenotropil in the rehabilitation of stroke patients — controlled clinical trialView study →.
This is mechanistically plausible — in rat cerebral-ischaemia models phenylpiracetam reduced neurological deficit, preserved memory and locomotor function, improved survival and helped restore local cerebral blood flow, outperforming piracetam 10Reference 10Comparative evaluation of the neuroprotective activity of phenotropil and piracetam in laboratory animals with experimental cerebral ischemia — comparative animal studyView study →.
The 2010 Drugs review places phenylpiracetam among the piracetam-like compounds with reported clinical use in stroke and cognitive impairment 1Reference 1ReviewPiracetam and piracetam-like drugs: from basic science to novel clinical applications to CNS disorders — reviewView study →.
Still, this rests on essentially one sizeable controlled trial from a single research tradition, with no Western replication.
Gap: A single unblinded controlled trial carries the whole clinical claim; no modern multicentre or placebo-controlled confirmation exists.
Beyond acute stroke, several Russian studies report benefit in chronic cerebrovascular conditions — vascular encephalopathy 9Reference 9Phenotropil in the treatment of vascular encephalopathy — comparative studyView study →, vertebrobasilar insufficiency 6Reference 6Clinical trialThe use of phenotropil in vertebrobasilar insufficiency — controlled clinical trialView study →, the consequences of organic brain lesions 21Reference 21The phenotropil treatment of the consequences of brain organic lesions — comparative studyView study →, and the chronic-brain-ischaemia population of the TRIUMPH asthenia program 3Reference 3Clinical trialTreatment of asthenic syndrome in patients with chronic brain ischemia: results of the non-interventional observational program TRIUMPH — observational studyView study →.
The proposed basis is a mix of neuroprotection, improved microcirculation and an antiaggregant (anti-platelet) effect: in hyperglycaemic rats phenylpiracetam normalised nitric-oxide-synthase function in platelets and vascular endothelium 14Reference 14AnimalA study of the mechanisms for antiaggregant activity of pyrrolidone derivatives in rats with chronic hyperglycemia — animal studyView study →.
The applications overlap heavily with the asthenia signal (the same patients, the same scales), so this is best read as part of one cerebrovascular story rather than an independent proof.
Gap: Comparative/observational designs, outcomes that blur into the asthenia endpoint, and no placebo-controlled data.
Unlike piracetam, phenylpiracetam has a genuine anticonvulsant action, identified in the original 1983 pharmacological characterisation of the molecule 15Reference 15Pharmacological characteristics of a new phenyl analog of piracetam — 4-phenylpiracetam — animal studyView study →.
This is also the one application with a properly blinded trial: a double-blind, placebo-controlled randomised study added phenotropil (100 or 200 mg) to standard antiepileptic drugs in 90 adults with symptomatic focal epilepsy, and reported reduced seizure frequency and improved cognition in the subgroup without epileptiform EEG abnormalities 19Reference 19RCTThe efficacy of add-on treatment with phenotropil in adult patients with locally-induced epilepsy — double-blind randomized placebo-controlled trialView study →.
A separate randomised comparative study in 75 patients with post-traumatic epilepsy found phenotropil (given with the antioxidant mexidol) potentiated antiepileptic drugs and improved cognition and mood without the seizure aggravation typical of many nootropics 20Reference 20RCTNootropics and antioxidants in the complex therapy of symptomatic posttraumatic epilepsy — randomized controlled trialView study →.
Further small Russian studies have used it as an add-on in symptomatic epilepsy and in complex epilepsy treatment 7,
Gap: Small samples, adjunct-only designs and Russian-language reporting; monotherapy efficacy is untested, and the blinded benefit was confined to a subgroup.
This is the reason most Western buyers take it, and it is the weakest-evidenced. The 2010 Drugs review notes phenylpiracetam’s greater potency and psychostimulant character but frames the clinical evidence as older, Russian and hard to verify 1Reference 1ReviewPiracetam and piracetam-like drugs: from basic science to novel clinical applications to CNS disorders — reviewView study →.
Animal work shows memory-enhancing and antidepressant effects, with the R-enantiomer specifically enhancing memory at 1 mg/kg while the S-enantiomer does not, despite similar brain concentrations — so the marketed racemate contains a memory-inactive half 11Reference 11Investigation into stereoselective pharmacological activity of phenotropil — comparative animal studyView study →.
There is no good modern randomised trial demonstrating cognitive benefit in healthy adults. The sharpest limiting finding is that in animals, nootropic effects track increases in hippocampal BDNF that appear only under conditions of cognitive deficiency, not in healthy high-performers 22Reference 22AnimalEffects of nootropic drugs on hippocampal and cortical BDNF levels in mice — animal studyView study →.
What users describe as “focus” is consistent with the drug’s DAT-inhibiting, mildly stimulant action rather than with any demonstrated nootropic effect in non-impaired brains.
Gap: No controlled trials in healthy people; the reputation is extrapolated from clinical (impaired) populations and animal models, and the animal mechanism itself is deficiency-dependent.
Phenylpiracetam’s “physical” reputation — endurance, stamina, tolerance to stress — is the least substantiated of all. It rests on the drug’s stimulant/DAT-inhibitor pharmacology 12Reference 12AnimalNeuroprotective and anti-inflammatory activity of DAT inhibitor R-phenylpiracetam in experimental models of inflammation in male mice — animal studyView study → and, circularly, on the fact that the World Anti-Doping Agency banned it as a stimulant in 1998 — the first nootropic ever prohibited in sport 17Reference 17ReviewUnauthorized ingredients in “nootropic” dietary supplements: a review of the history, pharmacology, prevalence, international regulations, and potential as doping agents — reviewView study →.
The doping-analysis literature that developed urine assays for carphedon describes it as “increasing physical endurance and cold resistance,” which is the origin of the athletic reputation 23Reference 23Determination of carphedon in human urine by solid-phase microextraction using capillary gas chromatography with nitrogen-phosphorus detection — analytical/doping studyView study → — but that is a characterisation in an analytical-methods paper, not a controlled performance trial. A ban confirms regulators judged it performance-relevant; it is not a demonstration of an ergogenic effect. No blinded trials of exercise performance in healthy athletes exist.
Gap: Essentially no controlled human performance data; the claim is inferred from mechanism and from its doping-list status.
Mechanisms
| Target / pathway | Effect | Relevant to |
|---|---|---|
| Dopamine transporter (DAT) | Selective inhibition (no NE/5-HT activity); raises synaptic dopamine | Stimulant feelfocusergogenic reputationmetabolic effects |
| Locomotor / behavioural activation | Increased (both enantiomers; R stronger) | Stimulant characterstamina reputation |
| Memory consolidation | Enhanced (R-enantiomer active at 1 mg/kg) | Cognitionanti-amnestic effect |
| Hippocampal BDNF | Increased — but only under cognitive deficiency | Cognition (deficiency-dependentnot in healthy brains) |
| Anticonvulsant action | Raises seizure threshold (absent in piracetam) | Epilepsy (adjunct) |
| Cerebral neuroprotection / microcirculation | Reduced ischaemic deficit, restored local blood flow | Strokecerebral ischaemia |
| Nitric-oxide synthase / platelet aggregation | Antiaggregant; normalised NOS in vessels | Cerebrovascular disease |
| Mitochondrial protection / anti-inflammatory | Reduced neuroinflammation (LPS model) | Ischaemianeurodegeneration (preclinical) |
| Glucose / leptin / body-weight regulation | S-enantiomer lowers weight gain, glucose, leptin (rodent) | Investigational metabolic-syndrome use |
Pharmacokinetics
Phenylpiracetam is orally active and lipophilic — the phenyl group improves blood–brain-barrier penetration relative to piracetam, which is why it works at lower doses (typically 100–200 mg vs piracetam’s grams). In rodents it reaches brain tissue within ~15 minutes of oral or intraperitoneal dosing, with brain concentrations of tens of µg/g 12Reference 12AnimalNeuroprotective and anti-inflammatory activity of DAT inhibitor R-phenylpiracetam in experimental models of inflammation in male mice — animal studyView study →. It is used clinically as a racemate, but the two enantiomers are not equivalent: the R-enantiomer carries most of the memory-enhancing activity despite similar brain concentrations, while both contribute to locomotor and antidepressant effects 11Reference 11Investigation into stereoselective pharmacological activity of phenotropil — comparative animal studyView study →. Human pharmacokinetic detail (half-life, metabolism, food effects) is poorly characterised in the accessible literature; the community-reported elimination half-life is roughly 3–5 hours, but this is not well documented in peer-reviewed sources. Tolerance to the stimulant effect develops quickly, which is consistently described by users and limits daily use.
Clinical trials
There is no registered trial activity on ClinicalTrials.gov for phenylpiracetam, carphedon, phenotropil or fonturacetam — the entire clinical record is Russian-language journal literature outside the international registry system, and the compound is off-patent with no Western industry sponsor.
| Completed | Planned | Terminated | Preclinical |
|---|---|---|---|
| 0(registered) | 0 | 0 | ~15+ |
Last checked: August 2026.
Dietary Sources
Phenylpiracetam has no dietary sources. It is a wholly synthetic molecule — piracetam with a phenyl group added to the 4-position of the pyrrolidinone ring — first synthesised in the Soviet Union in the 1980s 15Reference 15Pharmacological characteristics of a new phenyl analog of piracetam — 4-phenylpiracetam — animal studyView study →. It does not occur in food or in nature and cannot be obtained from diet, so there is no “eat more of X” alternative to supplementation.
How it’s made: it is produced synthetically from a phenyl-substituted γ-butyrolactam/pyrrolidinone intermediate; the marketed product is a racemate of R- and S-enantiomers, which differ pharmacologically (the R-enantiomer carries most of the memory-related activity) 11Reference 11Investigation into stereoselective pharmacological activity of phenotropil — comparative animal studyView study →. Note that, precisely because there is no dietary or agricultural source, everything sold is manufactured — and market-surveillance studies repeatedly find products labelled as containing phenylpiracetam that are mislabelled, under- or over-dosed, or contaminated with other unapproved drugs 16,
Dosage
Because phenylpiracetam is not a nutrient, there is no RDA/AI and no Tolerable Upper Intake Level — reference intake values do not exist for it. The doses below are the amounts studied in research or reported by users, not a personal recommendation.
| Context | Reported dose | Notes |
|---|---|---|
| Russian asthenia trials | 100–200 mg/day | Meta-analysis pooled the 200 mg/day dose; TRIUMPH used 100 mg/day 2, |
| Stroke rehabilitation trial | 400 mg/day (in courses) | Higher, supervised clinical dosing over a year 5Reference 5Clinical trialEfficacy of phenotropil in the rehabilitation of stroke patients — controlled clinical trialView study → |
| Adjunctive epilepsy trial | 100–200 mg/day | Added to standard antiepileptics in the double-blind study 19Reference 19RCTThe efficacy of add-on treatment with phenotropil in adult patients with locally-induced epilepsy — double-blind randomized placebo-controlled trialView study → |
| Community / “nootropic” use | 100–200 mg per dose | Often once daily; tolerance to the stimulant effect develops quickly, so continuous daily use loses effect |
Key intake points: doses are low compared with piracetam (milligrams vs grams) because the phenyl group improves brain penetration; the stimulant effect is best not taken late in the day (sleep disruption); and there is no established maximum safe intake, so higher-is-better reasoning is unwarranted.
Safety
Phenylpiracetam is generally described as low-acute-toxicity in its clinical use, but “few reported problems” is not the same as “shown to be safe” — and for this compound the most decision-relevant risks are regulatory and quality-control rather than pharmacological.
- Not an approved supplement or medicine in most Western countries. It is sold as a research chemical; nobody has evaluated the products on sale.
- Product quality is unreliable. One analysis found 75% of declared quantities inaccurate, with adulterants including phenibut, vinpocetine, picamilon and aniracetam.
- WADA-banned as a stimulant since 1998 — the first nootropic ever prohibited in sport. It will cause a positive in-competition test.
- Stimulant effects and rapid tolerance. Insomnia, over-arousal and irritability; the alerting effect fades quickly with continuous use.
- Interactions are unstudied, not absent. Combining a DAT inhibitor with other stimulants or dopaminergic drugs is a plausible concern that nobody has tested.
- No upper limit is set. It is not a nutrient; the absence of a UL says nothing about the safety of high doses.
Full Safety & Interactions Detail
- Stimulant effects: insomnia, over-arousal, irritability and, at high doses in the original animal work, paradoxical psychodepressant effects 15Reference 15Pharmacological characteristics of a new phenyl analog of piracetam — 4-phenylpiracetam — animal studyView study →. Rapid tolerance to the alerting effect is consistently reported.
- Regulatory / quality: it is not an approved dietary supplement or licensed medicine in most Western countries. Independent testing repeatedly finds products that are mislabelled, contain the wrong dose, or are adulterated with other unapproved drugs (phenibut, vinpocetine, picamilon, aniracetam, omberacetam) — in one analysis 75% of declared quantities were inaccurate 16Reference 16Five unapproved drugs found in cognitive enhancement supplementsView study →, and EU/Australian surveillance intercepted bulk raw phenylpiracetam on the illegal market 18Reference 18The occurrence of illicit smart drugs or nootropics in Europe and Australia and their associated dangers: results from a market surveillance study by 12 official medicines control laboratoriesView study →.
- Sport: phenylpiracetam is on the WADA Prohibited List as a stimulant (the first nootropic ever banned, in 1998) — it will cause a positive doping test in competition 17Reference 17ReviewUnauthorized ingredients in “nootropic” dietary supplements: a review of the history, pharmacology, prevalence, international regulations, and potential as doping agents — reviewView study →. Validated urine assays for carphedon have existed since the 1990s, so detection is routine 23Reference 23Determination of carphedon in human urine by solid-phase microextraction using capillary gas chromatography with nitrogen-phosphorus detection — analytical/doping studyView study →.
- Interactions: as a DAT inhibitor with stimulant activity, combining it with other stimulants (caffeine, amphetamines, decongestants) or with drugs affecting dopamine is a plausible concern, but specific drug-interaction studies have not been done and should not be assumed safe.
Scope disclosure. Interactions assessed? Partially — mechanism-level concerns are flagged, but no dedicated human drug-interaction studies exist. Pregnancy/lactation assessed? No human data. Upper limit established? No. Where phenylpiracetam has not been studied, that is stated rather than assumed benign.
Avoid. There are no human safety data in pregnancy or lactation for phenylpiracetam, it is a stimulant-like synthetic drug of uncertain product quality, and no regulatory body has evaluated it for this use. Absence of reports is not evidence of safety.
Related racetams: piracetam (the unsubstituted parent), aniracetam, oxiracetam, pramiracetam, coluracetam, fasoracetam and nefiracetam. Users commonly pair racetams with a choline donor such as citicoline, though this is convention rather than an evidence-based combination for phenylpiracetam specifically.
References
- Malykh AG, Sadaie MR (2010). Piracetam and piracetam-like drugs: from basic science to novel clinical applications to CNS disorders — review. Drugs, 70(3), 287–312. https://pubmed.ncbi.nlm.nih.gov/20166767/
- Devlikamova FI, Safina DR (2025). Efficacy and safety of fonturacetam in asthenia: a systematic review and meta-analysis. Zhurnal Nevrologii i Psikhiatrii im. S.S. Korsakova. https://pubmed.ncbi.nlm.nih.gov/40047835/
- Fedin AI, Solov’eva ÉI, Mironova OP, et al. (2014). Treatment of asthenic syndrome in patients with chronic brain ischemia: results of the non-interventional observational program TRIUMPH — observational study. Zhurnal Nevrologii i Psikhiatrii im. S.S. Korsakova. https://pubmed.ncbi.nlm.nih.gov/25726789/
- Gromova OA, Torshin IY (2024). Pharmacological effects of fonturacetam (Actitropil) and prospects for its clinical use — review. Zhurnal Nevrologii i Psikhiatrii im. S.S. Korsakova. https://pubmed.ncbi.nlm.nih.gov/39269293/
- Koval’chuk VV, Skoromets AA, Koval’chuk IV, et al. (2010). Efficacy of phenotropil in the rehabilitation of stroke patients — controlled clinical trial. Zhurnal Nevrologii i Psikhiatrii im. S.S. Korsakova. https://pubmed.ncbi.nlm.nih.gov/21626817/
- Liubimov AV (2013). The use of phenotropil in vertebrobasilar insufficiency — controlled clinical trial. Zhurnal Nevrologii i Psikhiatrii im. S.S. Korsakova. https://pubmed.ncbi.nlm.nih.gov/24430043/
- Poverennova IE, Iakunina AV, Kalinin VA, et al. (2011). Phenotropil in the complex treatment of symptomatic post-traumatic epilepsy. Zhurnal Nevrologii i Psikhiatrii im. S.S. Korsakova. https://pubmed.ncbi.nlm.nih.gov/23120795/
- Lybzikova GN, Iaglova ZhS, Kharlamova IuS (2008). The efficacy of phenotropil in the complex treatment of epilepsy — comparative study. Zhurnal Nevrologii i Psikhiatrii im. S.S. Korsakova. https://pubmed.ncbi.nlm.nih.gov/18646385/
- Gustov AA, Smirnov AA, Korshunova IuA, et al. (2006). Phenotropil in the treatment of vascular encephalopathy — comparative study. Zhurnal Nevrologii i Psikhiatrii im. S.S. Korsakova. https://pubmed.ncbi.nlm.nih.gov/16608112/
- Tiurenkov IN, Bagmetov MN, Epishina VV (2007). Comparative evaluation of the neuroprotective activity of phenotropil and piracetam in laboratory animals with experimental cerebral ischemia — comparative animal study. Eksperimental’naia i Klinicheskaia Farmakologiia. https://pubmed.ncbi.nlm.nih.gov/17523446/
- Zvejniece L, et al. (2011). Investigation into stereoselective pharmacological activity of phenotropil — comparative animal study. Basic & Clinical Pharmacology & Toxicology, 109(6). https://pubmed.ncbi.nlm.nih.gov/21689376/
- Zvejniece L, et al. (2020). Neuroprotective and anti-inflammatory activity of DAT inhibitor R-phenylpiracetam in experimental models of inflammation in male mice — animal study. Inflammopharmacology, 28. https://pubmed.ncbi.nlm.nih.gov/32279140/
- Zvejniece L, et al. (2017). S-phenylpiracetam, a selective DAT inhibitor, reduces body weight gain without influencing locomotor activity — animal study. Pharmacology, Biochemistry, and Behavior, 160. https://pubmed.ncbi.nlm.nih.gov/28743458/
- Zhilyuk VI, Levykh AE, Mamchur VI (2014). A study of the mechanisms for antiaggregant activity of pyrrolidone derivatives in rats with chronic hyperglycemia — animal study. Bulletin of Experimental Biology and Medicine, 157. https://pubmed.ncbi.nlm.nih.gov/24824701/
- Bobkov IuG, Morozov IS, Glozman OM, et al. (1983). Pharmacological characteristics of a new phenyl analog of piracetam — 4-phenylpiracetam — animal study. Biulleten’ Eksperimental’noi Biologii i Meditsiny. https://pubmed.ncbi.nlm.nih.gov/6403074/
- Cohen PA, et al. (2021). Five unapproved drugs found in cognitive enhancement supplements. Neurology: Clinical Practice, 11(3). https://pubmed.ncbi.nlm.nih.gov/34484905/
- Jędrejko K, Catlin O, Stewart T, et al. (2023). Unauthorized ingredients in “nootropic” dietary supplements: a review of the history, pharmacology, prevalence, international regulations, and potential as doping agents — review. Drug Testing and Analysis, 15. https://pubmed.ncbi.nlm.nih.gov/37357012/
- Vanhee C, Deconinck E, George M, et al. (2025). The occurrence of illicit smart drugs or nootropics in Europe and Australia and their associated dangers: results from a market surveillance study by 12 official medicines control laboratories. Journal of Xenobiotics, 15. https://pubmed.ncbi.nlm.nih.gov/40558871/
- Grebeniuk OV, Zhukova NG, Alifirova VM (2014). The efficacy of add-on treatment with phenotropil in adult patients with locally-induced epilepsy — double-blind randomized placebo-controlled trial. Zhurnal Nevrologii i Psikhiatrii im. S.S. Korsakova. https://pubmed.ncbi.nlm.nih.gov/25591651/
- Savenkov AA, Badalian OL, Avakian GN (2013). Nootropics and antioxidants in the complex therapy of symptomatic posttraumatic epilepsy — randomized controlled trial. Zhurnal Nevrologii i Psikhiatrii im. S.S. Korsakova. https://pubmed.ncbi.nlm.nih.gov/23887448/
- Savchenko AIu, Zakharova NS, Stepanov IN (2005). The phenotropil treatment of the consequences of brain organic lesions — comparative study. Zhurnal Nevrologii i Psikhiatrii im. S.S. Korsakova. https://pubmed.ncbi.nlm.nih.gov/16447562/
- Firstova IuIu, Dolotov OV, Kondrakhin eA, et al. (2009). Effects of nootropic drugs on hippocampal and cortical BDNF levels in mice — animal study. Eksperimental’naia i Klinicheskaia Farmakologiia. https://pubmed.ncbi.nlm.nih.gov/20095391/
- Kim S, Park JH, Myung SW, Lho DS (1999). Determination of carphedon in human urine by solid-phase microextraction using capillary gas chromatography with nitrogen-phosphorus detection — analytical/doping study. The Analyst, 124(11). https://pubmed.ncbi.nlm.nih.gov/10746314/
For half-lives, timing and stacking across the nootropics on this site, see the Nootropic Dosage Guide.



