
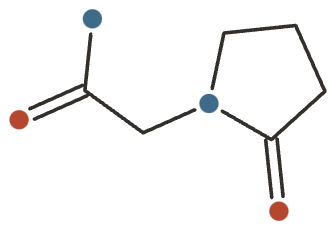

Piracetam at a Glance
Piracetam is the original nootropic — synthesised at UCB in Belgium in 1964, and the compound the word “nootropic” was coined to describe. It is a cyclic derivative of GABA built on a 2-pyrrolidinone ring, though it does not act on GABA receptors.
It is a prescription medicine in much of Europe, where its established use is cortical myoclonus, and it is the most-studied member of the racetam family by a wide margin.
What It’s Used For
- Cortical myoclonus — reduces involuntary muscle jerks; its approved indication.
- Age-related cognitive impairment & dementia — supports cognition in age-related decline.
- Dyslexia (children) — improves reading and verbal learning in dyslexic children.
- Post-stroke aphasia — aids language recovery after stroke.
- Post-surgical cognitive decline — used for cognitive decline after cardiac surgery.
- Healthy-user cognitive enhancement — the popular use, for memory and focus.
How It Works
Piracetam’s best-characterised action is physical rather than receptor-based: it binds phospholipid head groups in cell membranes and restores their fluidity. Ageing and injury make neuronal membranes more rigid, and piracetam’s effects track closely with reversing that — which explains why it does most in impaired tissue.
Downstream, it positively modulates AMPA receptors, facilitating long-term potentiation, and improves red-cell deformability, which raises microcirculatory blood flow. It is water-soluble, short-acting and dosed in grams, split across the day.
The full trial record is in Pharmacology & Research below.
Pharmacology & Research
Piracetam is the prototype racetam — a cyclic derivative of the neurotransmitter GABA, synthesized in 1964, and the compound that gave the word “nootropic” its meaning. It is purely synthetic: it does not occur in food or nature, so there is no dietary source and no deficiency to correct — and in much of Europe it is a licensed medicine (Nootropil), while in the United States it is neither an FDA-approved drug nor a lawful dietary-supplement ingredient, despite being sold as one 13Reference 13Presence of piracetam in cognitive enhancement dietary supplements — analytical studyView study →.
Its pharmacology is unusual: rather than binding a single receptor, it appears to restore neuronal membrane fluidity, which in turn modulates AMPA-glutamatergic and cholinergic signaling and improves mitochondrial function. That mechanism predicts its most consistent theme in the clinical literature — piracetam does the most where brain function is already impaired (aged/demented brains, cortical myoclonus, post-stroke rehabilitation) and very little in young, healthy, cognitively-intact users. The evidence base is large but old, mostly European, and much of it predates modern trial standards; effect sizes are generally modest and the strongest single indication (cortical myoclonus) is a neurological, not a “smart-drug,” use.
Support is an experimental score I’m building — a composite weighted by study type (human > animal > in vitro > review) and study volume. It’s a beta: a fast way to rank strength of evidence at a glance, not a validated metric. Each application links down to its write-up.
Piracetam’s most convincing indication is neurological, not cognitive. In a placebo-controlled, double-blind crossover trial of 21 patients with disabling cortical myoclonus (2.4–16.8 g/day, added to existing antimyoclonic drugs), motor, writing, functional-dizability and global scores all improved significantly on piracetam, with a median total-score improvement of ~22%; strikingly, 10 of 21 patients had to be rescued from the placebo phase for intolerable worsening while none needed rescue from piracetam 6Reference 6RCTEffectiveness of piracetam in cortical myoclonus — randomised crossover trialView study →.
An 18-month open-label study in progressive myoclonus epilepsy found the benefit was sustained and well tolerated 7Reference 7Long-term efficacy and safety of piracetam in the treatment of progressive myoclonus epilepsy — open-label studyView study →.
This is an adjunctive effect at high doses, not monotherapy.
Gap: small sample, almost always given on top of other antimyoclonic drugs, so piracetam’s stand-alone contribution is hard to isolate.
A systematic review and meta-analysis of 7 RCTs (261 patients total) found that piracetam produced no significant improvement in overall aphasia severity (SMD 0.23, 95% CI −0.03 to 0.49, P=0.08) but a significant benefit for written language (SMD 0.35, 95% CI 0.04 to 0.66, P=0.03) 3Reference 3Meta-analysisPiracetam for aphasia in post-stroke patients: a systematic review and meta-analysis of RCTs — meta-analysisView study →. The signal is strongest when piracetam is paired with intensive speech therapy: a PET study of 24 patients showed piracetam (2400 mg twice daily for 6 weeks) increased task-activated blood flow in language regions and aided rehabilitation 8Reference 8RCTPiracetam improves activated blood flow and facilitates rehabilitation of poststroke aphasic patients — RCTView study →.
Gap: small trials, benefit limited to a sub-domain (written language) and dependent on concurrent speech therapy; overall severity — the outcome that matters most to patients — did not improve significantly.
In a double-blind, placebo-controlled RCT of 98 patients undergoing coronary artery bypass grafting (CABG), piracetam (IV then 12 g/day orally for 6 weeks) significantly improved a combined score across 12 neuropsychological tests in the per-protocol population (effect 1.848, P=0.041), with a trend in the intent-to-treat population (P=0.064) 5Reference 5RCTPiracetam prevents cognitive decline in coronary artery bypass: a randomized trial versus placebo — RCTView study →.
Gap: a single trial, a specific surgical population, and a composite outcome that only reached significance per-protocol; needs replication.
Several small double-blind RCTs in the 1980s–90s tested piracetam (~3.3 g/day) in dyslexic children. One 12-week study in 55 boys reported gains on some reading and information-processing measures 9Reference 9Clinical trialEvaluation of the efficacy of piracetam in treating information processing, reading and writing disorders in dyslexic children — controlled clinical trialView study →; a 10-week study in 60 children found improvement concentrated in a “phonetic” subgroup rather than across the board 10Reference 10RCTA trial of piracetam in two subgroups of students with dyslexia — RCTView study →. Results are inconsistent and effects, where present, are small and subgroup-specific.
Gap: old, small, heterogeneous trials with inconsistent outcomes; no modern replication and piracetam is not used clinically for dyslexia today.
This is the use that drives piracetam’s popularity and has the weakest support. Pharmacological reviews and the classic overview note that measurable cognitive effects appear in impaired brains (aged, demented, injured) but are largely absent in young, healthy, cognitively-intact volunteers 15,
Gap: essentially no controlled evidence of benefit in healthy adults; the mechanism itself (restoring impaired membrane/mitochondrial function) predicts little to fix in a healthy brain.
Mechanisms
| Target / pathway | Effect | Relevant to |
|---|---|---|
| Neuronal membrane phospholipids | Restores membrane fluidity (binds polar head-groups); effect greater in aged membranes | Cognitive impairmentall CNS uses |
| Mitochondrial function | Enhances membrane potential and ATP synthesis, reduces apoptosis sensitivity | Aging/Alzheimer modelsneuroprotection |
| AMPA-type glutamate receptors | Positive modulation of glutamatergic transmission | Cognitionneuroplasticity |
| Cholinergic system | Modulates acetylcholine transmission | Memory & learning |
| Erythrocyte / vascular endothelium | Reduces RBC adhesion, hinders vasospasm, improves microcirculation | Strokesickle-cell (tested) |
Pharmacokinetics
Piracetam is a small, water-soluble molecule that is almost completely absorbed orally, reaches peak plasma concentration in roughly 1 hour, and is not metabolized — it is excreted essentially unchanged by the kidneys with a plasma half-life of about 4–5 hours 15,
Clinical trials
Piracetam has been studied for over five decades across dementia, stroke, myoclonus, aphasia, dyslexia and sickle-cell disease, but it is off-patent and generic, so there is little modern industry-sponsored trial activity; recent literature is dominated by preclinical mechanism (mitochondrial/membrane) and review papers rather than new large RCTs.
| Completed | Planned | Terminated | Preclinical |
|---|---|---|---|
| ~40+RCTs (mostly pre-2010) | Few | Rare | Many(ongoing membrane/mitochondrial work) |
Last checked: July 2026.
Dosage
These are doses studied in research, not a personal recommendation.
Piracetam is dosed in grams, not milligrams, reflecting its low potency:
| Use | Typical dose | Notes |
|---|---|---|
| Self-directed cognitive use | 1,600–4,800 mg/day, split into 2–3 doses | The range most nootropic users take; evidence of benefit in healthy people is weak 15Reference 15ReviewPiracetam: a review of pharmacological properties and clinical uses — reviewView study → |
| Age-related cognitive impairment (trials) | 2,400–4,800 mg/day | Doses used in the dementia/cognitive-impairment meta-analysis 1Reference 1Meta-analysisClinical efficacy of piracetam in cognitive impairment: a meta-analysis — meta-analysisView study → |
| Post-stroke aphasia (trials) | 4,800 mg/day (2,400 mg ×2) | With intensive speech therapy 8Reference 8RCTPiracetam improves activated blood flow and facilitates rehabilitation of poststroke aphasic patients — RCTView study → |
| Cortical myoclonus (medical) | 8–24 g/day, titrated | High-dose, physician-supervised, as add-on therapy 6, |
Piracetam is almost fully absorbed and does not require food; because it is renally excreted unchanged, doses should be reduced in renal impairment and it is not recommended in severe kidney disease. There is no established Upper Intake Level — it is not a nutrient — but multi-gram daily doses have been used safely in trials. The nootropic dosage guide sets this dose beside the rest of the racetam family and the choline sources usually taken with them.
Safety
Piracetam has one of the widest safety margins of any centrally-acting compound, and the practical limits are renal, not toxicological — it leaves the body unchanged through the kidneys, so impaired clearance is what actually constrains the dose.
- Very wide safety margin. Well tolerated even at high doses over long periods.
- Reduce or avoid in kidney disease. Excreted unchanged by the kidneys, so it accumulates in renal impairment.
- Avoid in pregnancy and breastfeeding. Crosses the placenta and enters milk, with no adequate data — see the box below.
- Mild antiplatelet effect. Take care with bleeding disorders, anticoagulants, and around surgery.
- Headache is the usual complaint. Often addressed by pairing with a choline source such as alpha-GPC or CDP-choline.
Full Safety & Interactions Detail
Piracetam has one of the widest safety margins of any centrally-acting compound and is well tolerated even at high doses over long periods 7,
The most common adverse effect is mild headache, which many users attribute to increased acetylcholine turnover and address by pairing piracetam with a choline source (alpha-GPC or CDP-choline). Other reported effects — generally mild and dose-related — include agitation, irritability, anxiety, insomnia and, occasionally, gastrointestinal upset. Because it can have mild antiplatelet/antithrombotic effects, caution is warranted in people with bleeding disorders or on anticoagulants, and around surgery.
The dose-limiting consideration in practice is renal clearance: piracetam is excreted unchanged by the kidneys, so it accumulates in renal impairment and doses must be reduced or the drug avoided. It should be used cautiously in people with kidney disease.
Avoid. Piracetam crosses the placenta and is excreted into breast milk, and there is no adequate safety data in pregnant or breastfeeding women. There is no established benefit that would justify the unknown risk, so the prudent verdict is to avoid it during pregnancy and lactation.
References
- Waegemans, T., et al. (2002). Clinical efficacy of piracetam in cognitive impairment: a meta-analysis — meta-analysis. Dementia and Geriatric Cognitive Disorders. https://pubmed.ncbi.nlm.nih.gov/12006732/
- Müller, W. E., et al. (1999). Piracetam: novelty in a unique mode of action — review. Pharmacopsychiatry. https://pubmed.ncbi.nlm.nih.gov/10338102/
- Zhang, J., et al. (2017). Piracetam for aphasia in post-stroke patients: a systematic review and meta-analysis of RCTs — meta-analysis. CNS Drugs. https://pubmed.ncbi.nlm.nih.gov/27236454/
- Ricci, S., et al. (2012). Piracetam for acute ischaemic stroke — systematic review (Cochrane). Cochrane Database of Systematic Reviews. https://pubmed.ncbi.nlm.nih.gov/22972044/
- Szalma, I., et al. (2006). Piracetam prevents cognitive decline in coronary artery bypass: a randomized trial versus placebo — RCT. The Annals of Thoracic Surgery. https://pubmed.ncbi.nlm.nih.gov/16996947/
- Brown, P., et al. (1993). Effectiveness of piracetam in cortical myoclonus — randomised crossover trial. Movement Disorders. https://pubmed.ncbi.nlm.nih.gov/8419809/
- Fedi, M., et al. (2001). Long-term efficacy and safety of piracetam in the treatment of progressive myoclonus epilepsy — open-label study. Archives of Neurology. https://pubmed.ncbi.nlm.nih.gov/11346373/
- Kessler, J., et al. (2000). Piracetam improves activated blood flow and facilitates rehabilitation of poststroke aphasic patients — RCT. Stroke. https://pubmed.ncbi.nlm.nih.gov/10978039/
- Tallal, P., et al. (1986). Evaluation of the efficacy of piracetam in treating information processing, reading and writing disorders in dyslexic children — controlled clinical trial. International Journal of Psychophysiology. https://pubmed.ncbi.nlm.nih.gov/3522509/
- Ackerman, P. T., et al. (1992). A trial of piracetam in two subgroups of students with dyslexia — RCT. Journal of Learning Disabilities. https://pubmed.ncbi.nlm.nih.gov/1765729/
- Malykh, A. G., & Sadaie, M. R. (2010). Piracetam and piracetam-like drugs: from basic science to novel clinical applications to CNS disorders — systematic review. Drugs. https://pubmed.ncbi.nlm.nih.gov/20166767/
- Leuner, K., et al. (2011). Improved mitochondrial function in brain aging and Alzheimer disease — the new mechanism of action of piracetam — review. Frontiers in Neuroscience. https://pubmed.ncbi.nlm.nih.gov/20877425/
- Cohen, P. A., et al. (2020). Presence of piracetam in cognitive enhancement dietary supplements — analytical study. JAMA Internal Medicine. https://pubmed.ncbi.nlm.nih.gov/31764936/
- Al Hajeri, A., & Fedorowicz, Z. (2016). Piracetam for reducing the incidence of painful sickle cell disease crises — systematic review (Cochrane). Cochrane Database of Systematic Reviews. https://pubmed.ncbi.nlm.nih.gov/26869149/
- Winblad, B. (2005). Piracetam: a review of pharmacological properties and clinical uses — review. CNS Drug Reviews. https://pubmed.ncbi.nlm.nih.gov/16007238/
- Perng, C. H., et al. (2018). The treatment of cognitive dysfunction in dementia: a multiple treatments meta-analysis — meta-analysis. Psychopharmacology. https://pubmed.ncbi.nlm.nih.gov/29502274/
- Viana, M. B., et al. (2009). Painful crises in children with sickle cell disease are not prevented by piracetam — RCT. Acta Haematologica. https://pubmed.ncbi.nlm.nih.gov/19246889/
For half-lives, timing and stacking across the nootropics on this site, see the Nootropic Dosage Guide.



