
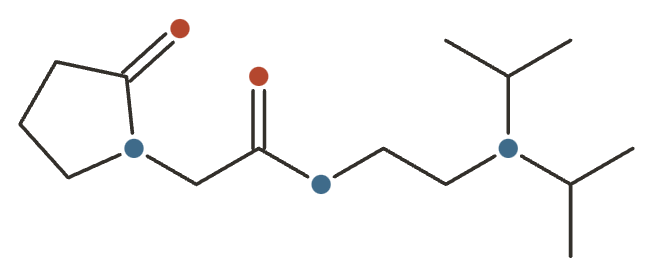

Pramiracetam at a Glance
Pramiracetam is a synthetic, fat-soluble racetam nootropic derived from piracetam, the original compound in the racetam family. It was developed in the late 1970s as CI-879 and shares the core 2-pyrrolidinone ring common to all racetams. In a few countries it is sold as a prescription medicine under the brand name Pramistar, marketed for age-related memory problems. It is often described as one of the more potent racetams by weight.
It is wholly synthetic, with no dietary source, and is supplied as pramiracetam sulphate — a salt, so labelled milligram amounts refer to the salt unless stated otherwise.
Pharmacologically there is no deficiency to correct here; every effect is an extra laid on a normal system. And the evidence has a clear centre of gravity: it sits in impaired brains — head injury, drug-induced amnesia — rather than healthy ones. That distinction is the most important thing here, because everyday cognitive enhancement is by far the dominant real-world use and by far the least supported.
The honest bottom line: a modest, dated evidence base for memory recovery after brain injury, a documented failure in Alzheimer’s disease, and essentially nothing controlled in healthy adults.
What It’s Used For
In the nootropic community, pramiracetam is taken for memory, learning, and sustained focus. Ranked by how well the evidence actually holds up:
- Traumatic brain injury and anoxia — the strongest human signal, from a double-blind RCT showing clinically meaningful delayed-recall gains that persisted for 18 months.
- Scopolamine-induced amnesia — a genuine controlled effect in healthy volunteers, but against an artificial model of cholinergic blockade.
- Age-related memory complaints — one small open-label pilot.
- Cerebrovascular memory disorders — the marketed Pramistar indication, resting on non-blinded data.
- Alzheimer’s disease — a well-documented failure, worth stating plainly.
Be sceptical of the everyday “study aid” use. There is essentially no controlled evidence for cognitive enhancement in healthy adults, which is the largest use case by far. In the United States, pramiracetam is not an approved drug and is not a permitted dietary-supplement ingredient — it is sold in a regulatory grey area rather than as a vetted supplement, so what is in the bottle is its own question.
How It Works
Pramiracetam works mainly by enhancing high-affinity choline uptake in the hippocampus, a brain region central to memory. By increasing how much choline neurons take up, it raises the raw material available for making acetylcholine, the neurotransmitter tied to learning and memory. This is also the practical basis for pairing it with a choline source — and the likeliest reason headache is its most common side effect.
What makes it unusual is what it doesn’t do: it has no measurable affinity for any classical neurotransmitter receptor — not adrenergic, muscarinic, serotonergic, dopaminergic, opioid, GABA or glutamate 8Reference 8ReviewPiracetam and other structurally related nootropics — reviewView study →. It appears to potentiate neurotransmission that is already happening rather than switching anything on directly, which is the leading view of the racetam class generally.
Because it is fat-soluble, it is absorbed better when taken with dietary fat. One further wrinkle explains some of the variability people report: the memory effect appears steroid-sensitive — elevated corticosteroids block the memory benefit of pramiracetam and related nootropics in rodents, which has been proposed as a reason clinical response differs so much between individuals 17Reference 17AnimalElevated corticosteroid levels block the memory-improving effects of nootropics and cholinomimetics — mouseView study →.
Pharmacology & Research
Pramiracetam is a synthetic, fat-soluble racetam nootropic (a 2-pyrrolidinone derivative developed as CI-879 in the early 1980s) marketed in a few countries as the prescription memory drug Pramistar. Its evidence base is small, old, and skewed toward impaired brains rather than healthy ones: the cleanest human signal is in traumatic brain injury and in pharmacologically-induced amnesia, not in cognitively normal people looking for an edge. Mechanistically it is unusual — it binds no known neurotransmitter receptor and appears to act indirectly by increasing high-affinity choline uptake, which is also why users pair it with a choline source. Because it is lipophilic, absorption improves with dietary fat, and the studied doses are gram-scale rather than milligram-scale. Treat the online reputation for dramatic cognitive enhancement with scepticism: it rests on a handful of dated trials and a great deal of extrapolation from rodent maze studies 15Reference 15AnimalThe effect of pramiracetam (CI-879) on the acquisition of a radial arm maze task — ratView study →.
Support is an experimental score I’m building — a composite weighted by study type (human > animal > in vitro > review) and study volume. It’s a beta: a fast way to rank strength of evidence at a glance, not a validated metric. Each application links down to its write-up.
The strongest human evidence. In a double-blind, placebo-controlled trial, young men with memory and cognitive deficits after brain injury took 400 mg pramiracetam sulphate three times daily; performance on memory measures — especially delayed recall — improved to a clinically significant degree versus placebo, and the gains were maintained across an 18-month open-label period and a 1-month post-discontinuation follow-up 1Reference 1RCTPlacebo-controlled study of pramiracetam in young males with memory and cognitive problems resulting from head injury and anoxia — randomised controlled trialView study →.
A later comparative trial in mild concussion reported better recovery of orientation and amnesia with pramiracetam (as Pramistar) than with piracetam 2Reference 2Clinical trialApplication of nootropic agents in complex treatment of patients with concussion of the brain — clinical trial, comparative studyView study →, and a systematic review notes it “reportedly improved cognitive deficits associated with traumatic brain injuries” 7Reference 7Systematic reviewPiracetam and piracetam-like drugs: from basic science to novel clinical applications to CNS disorders — systematic reviewView study →.
The effect is seen in injured brains, and the pivotal trial was small.
Gap: a single small RCT (plus one comparative study) carries this indication; there is no modern, adequately-powered replication.
In a randomised, placebo-controlled study, two groups of twelve men (ages 18–42 and 55–65) took 600 mg twice daily for 10 days; on day 11 scopolamine was used to induce amnesia. Pramiracetam partially reduced the scopolamine-induced impairment of episodic memory and selective attention in both age groups versus placebo 3Reference 3RCTPramiracetam effects on scopolamine-induced amnesia in healthy volunteers — randomised controlled trialView study →.
This is a genuine controlled human effect, but scopolamine-challenge is an artificial model of cholinergic blockade — it demonstrates a cholinergic mechanism more than it predicts real-world memory gains.
Gap: the endpoint is a drug-induced amnesia model in healthy people, not spontaneous cognitive performance; it does not establish enhancement in unimpaired users.
This is the marketed indication for Pramistar. An evaluation study in patients with chronic cerebrovascular insufficiency and stroke sequelae reported a “statistically significant heterogeneous influence” of pramiracetam monotherapy on memory symptoms 5Reference 5Clinical trialExperience in the application of pramistar, a new nootropic preparation, in the treatment of memory disorders in patients with cerebrovascular pathology — evaluation studyView study →. The methodology is weak — a non-blinded clinical-experience report rather than a rigorous RCT.
Gap: the data underpinning the approved use are observational/comparative and not placebo-controlled; effect sizes and durability are poorly characterised.
A negative result worth stating plainly, because it constrains how far the memory story generalises. Using an enrichment design — identifying apparent responders, then re-testing them under controlled conditions — a controlled trial of pramiracetam at doses up to 4,000 mg/day concluded the drug was unlikely to confer symptomatic benefit in Alzheimer’s disease: only 2 of 8 initial responders replicated their response on retesting 6Reference 6Clinical trialNootropic drugs in Alzheimer’s disease: symptomatic treatment with pramiracetam — controlled clinical trialView study →.
Enhancing cholinergic supply is evidently not sufficient once the cholinergic neurons themselves are degenerating.
Gap: none material to the conclusion — this is a clean negative. It does not rule out benefit in non-degenerative memory impairment, which is where the positive data sit.
Mechanisms
| Target / pathway | Effect | Relevant to |
|---|---|---|
| High-affinity choline uptake (HACU), hippocampus | ↑ (inverted-U dose response) 12Reference 12In vitroThe effects of various cognition-enhancing drugs on in vitro rat hippocampal synaptosomal sodium-dependent high-affinity choline uptake — in vitroView study → | Memory applications; rationale for choline co-supplementation |
| Choline transport across the blood–brain barrier | ↑; reverses scopolamine-induced changes 13Reference 13AnimalReversal of scopolamine-induced alterations of choline transport across the blood-brain barrier by the nootropics piracetam and pramiracetam — ratView study → | Scopolamine-amnesia effect |
| Neuronal nitric oxide synthase (cerebral cortex) | ↑ ~20% at high dose in rat 14Reference 14AnimalSystemic administration of pramiracetam increases nitric oxide synthase activity in the cerebral cortex of the ratView study → | Proposed learning/memory contribution |
| Cerebral blood flow | ↑ 13Reference 13AnimalReversal of scopolamine-induced alterations of choline transport across the blood-brain barrier by the nootropics piracetam and pramiracetam — ratView study → | General “cerebroactive” profile |
| Classical neurotransmitter receptors (adrenergic, muscarinic, 5-HT, dopamine, adenosine, opioid, GABA, benzodiazepine, glutamate) | No measurable affinity 8Reference 8ReviewPiracetam and other structurally related nootropics — reviewView study → | Explains lack of direct receptor-mediated effects |
The racetam class has no single agreed mechanism; the leading view is potentiation of existing neurotransmission (modulated ion flux) rather than direct receptor agonism 8Reference 8ReviewPiracetam and other structurally related nootropics — reviewView study →. Note that the memory effect appears steroid-sensitive — elevated corticosteroids block the memory benefit of pramiracetam and related nootropics in rodents, which has been proposed to explain variable clinical response 17Reference 17AnimalElevated corticosteroid levels block the memory-improving effects of nootropics and cholinomimetics — mouseView study →.
Pharmacokinetics
Oral pramiracetam is absorbed rapidly, with peak plasma concentrations at 2–3 hours 9Reference 9RCTPharmacokinetics of oral pramiracetam in normal volunteers — randomised controlled tolerance studyView study →. In a dose-ranging tolerance RCT (400–1,600 mg), AUC and Cmax rose linearly with dose while clearance and volume of distribution were dose-independent — clean first-order kinetics — and no significant side effects were seen at any dose 9Reference 9RCTPharmacokinetics of oral pramiracetam in normal volunteers — randomised controlled tolerance studyView study →. The elimination half-life is roughly 4.5–6.5 hours (harmonic mean), but between-subject variability is wide (individual values 2–8 hours) 9,
Clinical trials
Registered-trial activity is effectively nil: a ClinicalTrials.gov search returns no registered pramiracetam studies. The human evidence is a small set of trials conducted largely in the 1980s–2000s; as an off-patent compound with no active sponsor, it attracts no modern industry trial programme.
| Completed | Planned | Terminated | Preclinical |
|---|---|---|---|
| ~6(human RCT/controlled + PK) | 0 | 0 | ~25+ |
Last checked: August 2026.
Dietary Sources
Pramiracetam is a wholly synthetic molecule — it does not occur in food and has no dietary source, so there is no RDA/AI or food-based intake to report. It was synthesised as part of a medicinal-chemistry series of N-substituted 2-oxo-1-pyrrolidineacetamides and selected for development as CI-879 on the basis of its amnesia-reversal activity and wide animal safety margin 16Reference 16Amnesia-reversal activity of a series of N-[(disubstituted-amino)alkyl]-2-oxo-1-pyrrolidineacetamides, including pramiracetam — medicinal chemistry / discoveryView study →. It is supplied as pramiracetam sulphate (a salt); the counter-ion contributes to the compound’s total weight, so labelled milligram amounts refer to the salt unless stated otherwise.
Dosage
There is no established dietary requirement or Tolerable Upper Intake Level — pramiracetam is a drug/nootropic, not a nutrient. The doses studied in research and used in the nootropic community are gram-scale:
| Regimen | Amount | Source |
|---|---|---|
| Pivotal TBI RCT | 400 mg three times daily (1,200 mg/day) | 1Reference 1RCTPlacebo-controlled study of pramiracetam in young males with memory and cognitive problems resulting from head injury and anoxia — randomised controlled trialView study → |
| Scopolamine-amnesia RCT | 600 mg twice daily (1,200 mg/day) | 3Reference 3RCTPramiracetam effects on scopolamine-induced amnesia in healthy volunteers — randomised controlled trialView study → |
| PK tolerance study | single doses 400–1,600 mg, no significant side effects | 9Reference 9RCTPharmacokinetics of oral pramiracetam in normal volunteers — randomised controlled tolerance studyView study → |
Practical notes: pramiracetam is fat-soluble, so it is taken with dietary fat to aid absorption; kinetics are linear over the studied range, and the short half-life is the rationale for split dosing (two to three times daily) 9,
Safety
Short-term tolerability is good, and the honest caveats are about what hasn’t been studied rather than about demonstrated harm.
- Clean acute tolerability. Human PK/tolerance studies reported no significant side effects across single doses up to 1,600 mg, and animal work showed a wide safety margin 9,
16Reference 9RCTPharmacokinetics of oral pramiracetam in normal volunteers — randomised controlled tolerance studyView study →Reference 16Amnesia-reversal activity of a series of N-[(disubstituted-amino)alkyl]-2-oxo-1-pyrrolidineacetamides, including pramiracetam — medicinal chemistry / discoveryView study → . - Headache is the common complaint. Usually attributed to increased choline demand — the reason users pair it with a choline source.
- Occasional irritability at higher doses.
- Long-term human safety is not established. The trials are short; nothing characterises years of use.
- Unregulated supply. Not an approved drug or permitted dietary-supplement ingredient in the US, so product identity and purity are not guaranteed.
- No upper limit is set. It is not a nutrient; acute tolerance to 1,600 mg says nothing about a long-term ceiling.
Full Safety & Interactions Detail
Animal studies showed a wide margin of safety, and human PK/tolerance studies reported no significant side effects across single doses up to 1,600 mg 9,
Reported adverse effects in use are generally mild — most commonly headache (often attributed to increased choline demand, hence the practice of pairing with a choline source) and occasional irritability. The dose-limiting practical issue is not toxicity per se but the absence of long-term human safety data and the unregulated supply: pramiracetam is not an approved drug or permitted dietary-supplement ingredient in the US, so product identity and purity are not guaranteed.
Scope disclosure. Interactions assessed? Partially — the main mechanistically-plausible interaction is with cholinergic drugs and choline supplements (additive cholinergic load, headache) and, in theory, other centrally-acting agents. No systematic drug-interaction studies were identified, and no CYP450 interaction data were located. Pregnancy/lactation assessed? No — not studied. Upper limit established? No. Where pramiracetam has not been studied — long-term use, pregnancy, drug interactions — that is a data gap, not a clean bill of health.
Avoid. Safety in pregnancy and breastfeeding has not been established — there are no human reproductive-safety data. Absence of reported harm is not evidence of safety.
Related racetams: piracetam (the prototype it is derived from), aniracetam, oxiracetam, phenylpiracetam, coluracetam, fasoracetam and nefiracetam. The usual stack partner is a choline donor such as citicoline.
References
- McLean A, et al. (1991). Placebo-controlled study of pramiracetam in young males with memory and cognitive problems resulting from head injury and anoxia — randomised controlled trial. Brain Injury. https://pubmed.ncbi.nlm.nih.gov/1786500/
- Tkachev AV (2007). Application of nootropic agents in complex treatment of patients with concussion of the brain — clinical trial, comparative study. Likars’ka Sprava. https://pubmed.ncbi.nlm.nih.gov/18418926/
- Mauri M, et al. (1994). Pramiracetam effects on scopolamine-induced amnesia in healthy volunteers — randomised controlled trial. Archives of Gerontology and Geriatrics. https://pubmed.ncbi.nlm.nih.gov/15374306/
- De Vreese LP, et al. (1996). Memory training and drug therapy act differently on memory and metamemory functioning: evidence from a pilot study. Archives of Gerontology and Geriatrics. https://pubmed.ncbi.nlm.nih.gov/18653001/
- Dziak LA, Golik VA, Miziakina EV (2003). Experience in the application of pramistar, a new nootropic preparation, in the treatment of memory disorders in patients with cerebrovascular pathology — evaluation study. Likars’ka Sprava. https://pubmed.ncbi.nlm.nih.gov/14965012/
- Claus JJ, et al. (1991). Nootropic drugs in Alzheimer’s disease: symptomatic treatment with pramiracetam — controlled clinical trial. Neurology. https://pubmed.ncbi.nlm.nih.gov/2011259/
- Malykh AG, Sadaie MR (2010). Piracetam and piracetam-like drugs: from basic science to novel clinical applications to CNS disorders — systematic review. Drugs. https://pubmed.ncbi.nlm.nih.gov/20166767/
- Gouliaev AH, Senning A (1994). Piracetam and other structurally related nootropics — review. Brain Research Reviews. https://pubmed.ncbi.nlm.nih.gov/8061686/
- Chang T, et al. (1985). Pharmacokinetics of oral pramiracetam in normal volunteers — randomised controlled tolerance study. Journal of Clinical Pharmacology. https://pubmed.ncbi.nlm.nih.gov/4008675/
- Auteri A, et al. (1992). Pharmacokinetics of pramiracetam in healthy volunteers after oral administration. International Journal of Clinical Pharmacology Research. https://pubmed.ncbi.nlm.nih.gov/1473879/
- Fang Z, Liu X, Xiao Y, et al. (1999). Pharmacokinetics of pramiracetam in animals. Journal of West China University of Medical Sciences. https://pubmed.ncbi.nlm.nih.gov/11387954/
- Shih YH, Pugsley TA (1985). The effects of various cognition-enhancing drugs on in vitro rat hippocampal synaptosomal sodium-dependent high-affinity choline uptake — in vitro. Life Sciences. https://pubmed.ncbi.nlm.nih.gov/2987637/
- Brust P, et al. (1989). Reversal of scopolamine-induced alterations of choline transport across the blood-brain barrier by the nootropics piracetam and pramiracetam — rat. Arzneimittel-Forschung. https://pubmed.ncbi.nlm.nih.gov/2610714/
- Corasaniti MT, et al. (1995). Systemic administration of pramiracetam increases nitric oxide synthase activity in the cerebral cortex of the rat. Functional Neurology. https://pubmed.ncbi.nlm.nih.gov/8557218/
- Murray CL, Fibiger HC (1986). The effect of pramiracetam (CI-879) on the acquisition of a radial arm maze task — rat. Psychopharmacology. https://pubmed.ncbi.nlm.nih.gov/3088666/
- Butler DE, et al. (1984). Amnesia-reversal activity of a series of N-[(disubstituted-amino)alkyl]-2-oxo-1-pyrrolidineacetamides, including pramiracetam — medicinal chemistry / discovery. Journal of Medicinal Chemistry. https://pubmed.ncbi.nlm.nih.gov/6716406/
- Mondadori C, et al. (1992). Elevated corticosteroid levels block the memory-improving effects of nootropics and cholinomimetics — mouse. Psychopharmacology. https://pubmed.ncbi.nlm.nih.gov/1410129/
For half-lives, timing and stacking across the nootropics on this site, see the Nootropic Dosage Guide.



